Opening requested calculation...
Please wait, this takes like 47 seconds. Thank you for your patience! :)
☠
0 humans have been terminated by curable diseases since this page started loading
The Oxford RECOVERY trial isn’t theory. It’s proof.
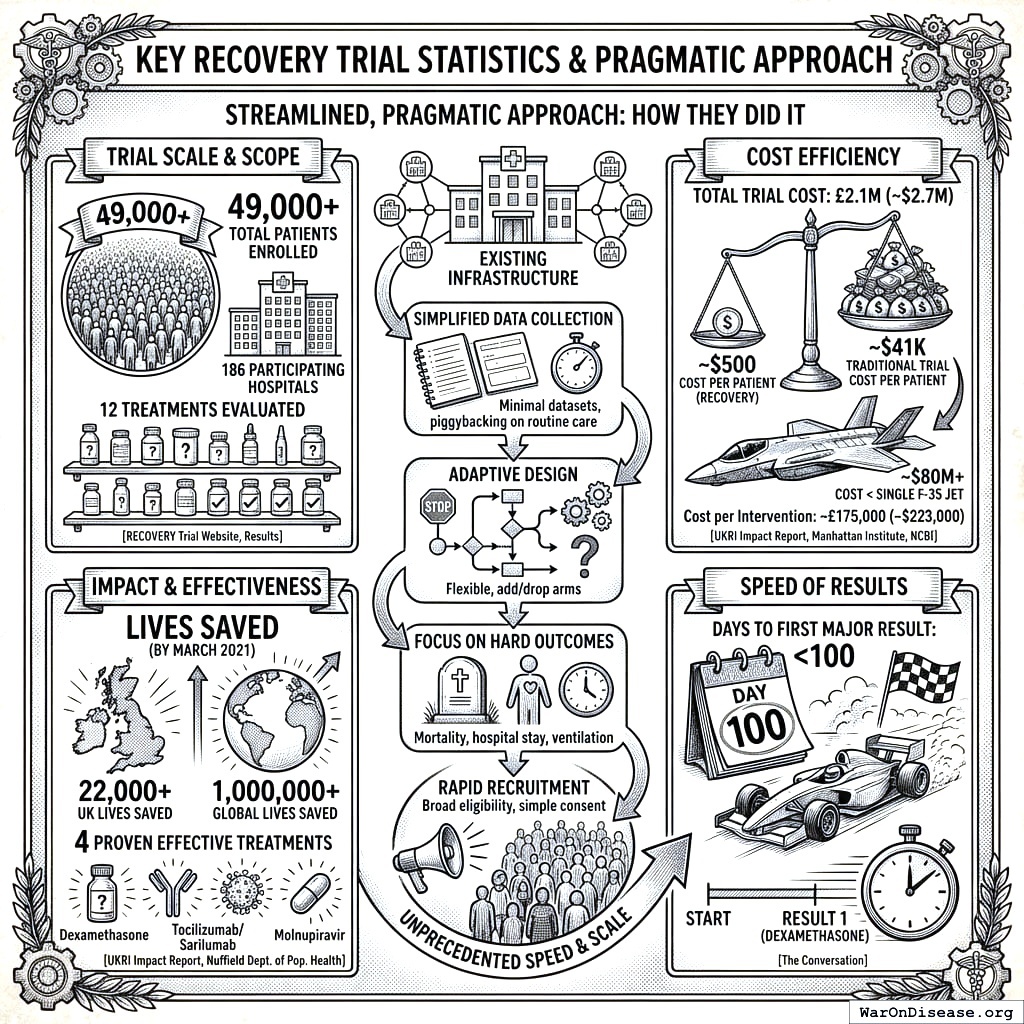
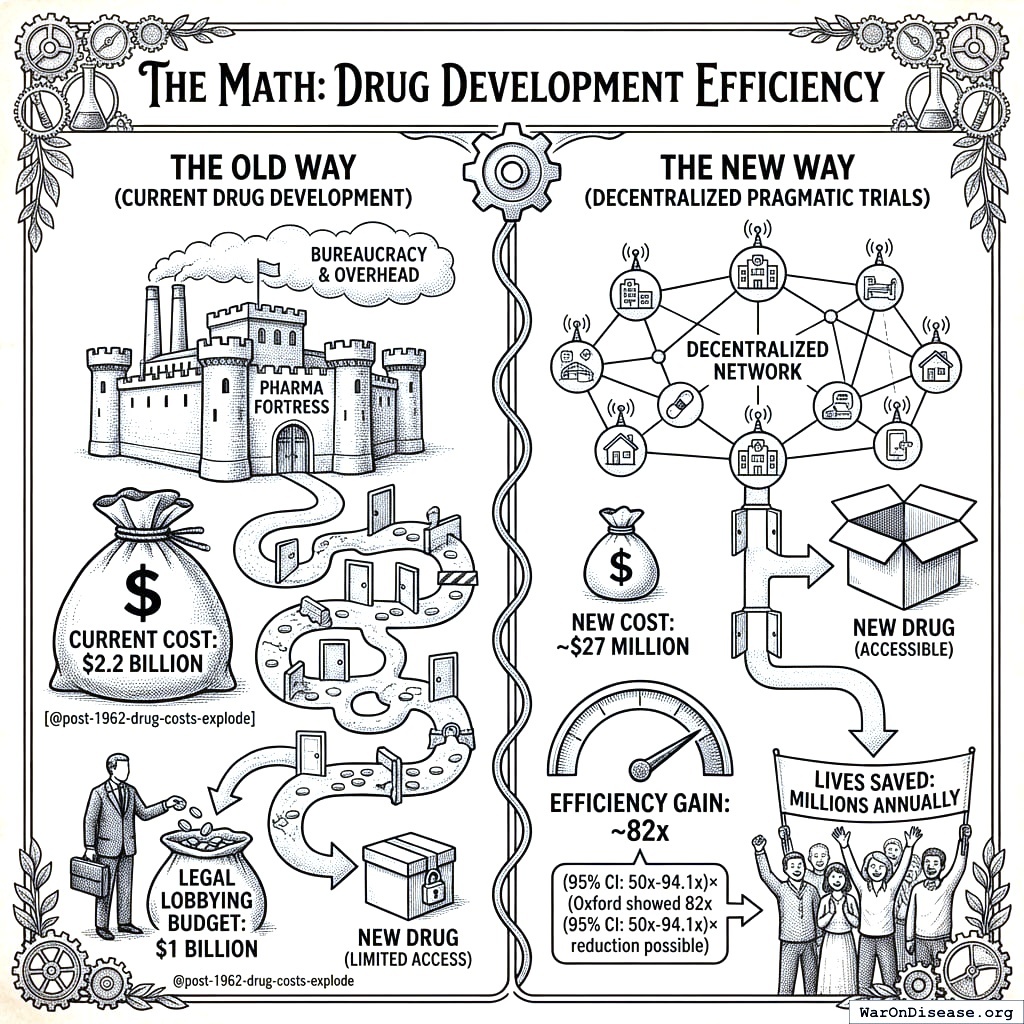
In 2020, Oxford spent $500 (95% CI: $400-$2,500) per patient1. Traditional trials cost $41,000 (95% CI: $20,000-$120,000). RECOVERY saved over 1 million lives2. That’s an 82x (90% CI: 21.4x-195x) efficiency gain.
| Conception to first patient |
9 days3 |
6-12 months4 |
| First life-saving result |
100 days5 |
6-10 years6 |
| Cost per life saved |
$2,700 |
Often never saves any lives |
Pragmatic vs Traditional Trials
| Cost per Patient |
$500 (95% CI: $400-$2,500) |
$41,000 (95% CI: $20,000-$120,000) |
| Time to Results |
Weeks to months |
5-7 years average |
| Participants |
Large (49,000+ in RECOVERY) |
Typically 500-3,000 |
| Implementation Speed |
Hours to days |
Months to years |
| Patient Population |
Diverse, real-world |
Highly selected |
| Setting |
Routine clinical practice |
Specialized research centers |
| Generalizability |
High |
Limited |
Key RECOVERY Trial Statistics
| Total Patients Enrolled |
49,000+ |
RECOVERY Trial Website7 |
| Participating Hospitals |
186 |
RECOVERY Trial Website7 |
| Total Trial Cost |
£2.1M (~$2.7M) |
UKRI Impact Report8 |
| Cost per Patient |
~$500 (95% CI: $400-$2,500)9 |
Manhattan Institute9 |
| Traditional Trial Cost per Patient |
~$41,000 (95% CI: $20,000-$120,000) |
NCBI1 |
| Treatments Evaluated |
12 |
RECOVERY Results10 |
| Cost per Intervention |
~£175,000 (~$223,000) |
Calculated (£2.1M ÷ 12 treatments) |
| Proven Effective Treatments |
4 |
Nuffield Department of Population Health11 |
| UK Lives Saved (by March 2021) |
22,000+ |
UKRI Impact Report8 |
| Global Lives Saved (by March 2021) |
1,000,000+ |
UKRI Impact Report8 |
| Days to First Major Result |
<100 |
The Conversation12 |
The RECOVERY trial enrolled 49,000 patients across 186 hospitals, tested 12 treatments, saved a million lives, and cost less than a single F-35 fighter jet.
How? Five obvious things:
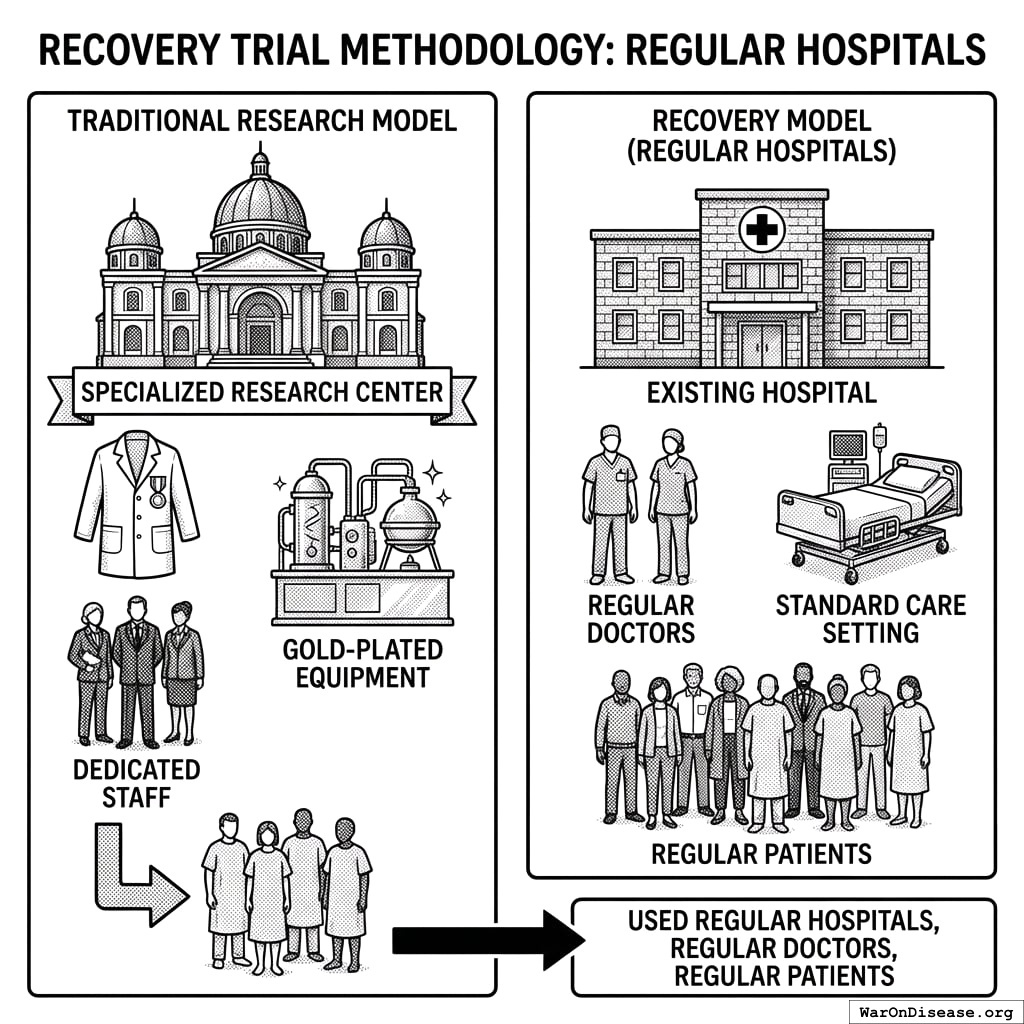
They Used Regular Hospitals
No specialized research centers. No gold-plated equipment. Just regular hospitals with regular doctors treating regular patients.
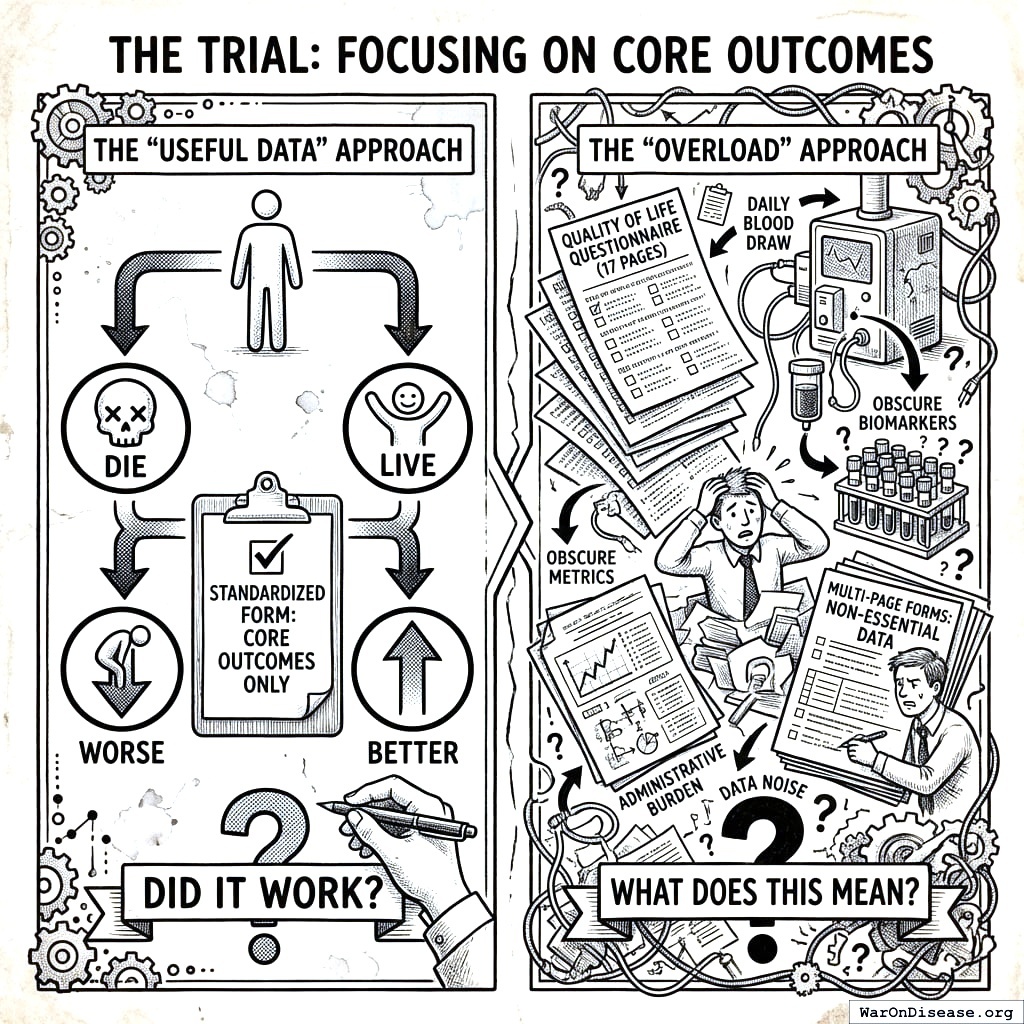
They Collected Only Useful Data
The trial focused on core outcomes: “Did the patient live or die? Did they get better or worse?”
No seventeen-page questionnaires about quality of life. No daily blood draws for biomarkers nobody understands. Just: “Did it work?”
They used existing hospital data. One standardized form. Done.
They Integrated With Normal Care
Patients got the experimental treatment during regular care. No separate facility. No hovering clipboard researchers. Just normal doctors, except some patients got the experimental drug.
Turns out this works fine. Who knew.
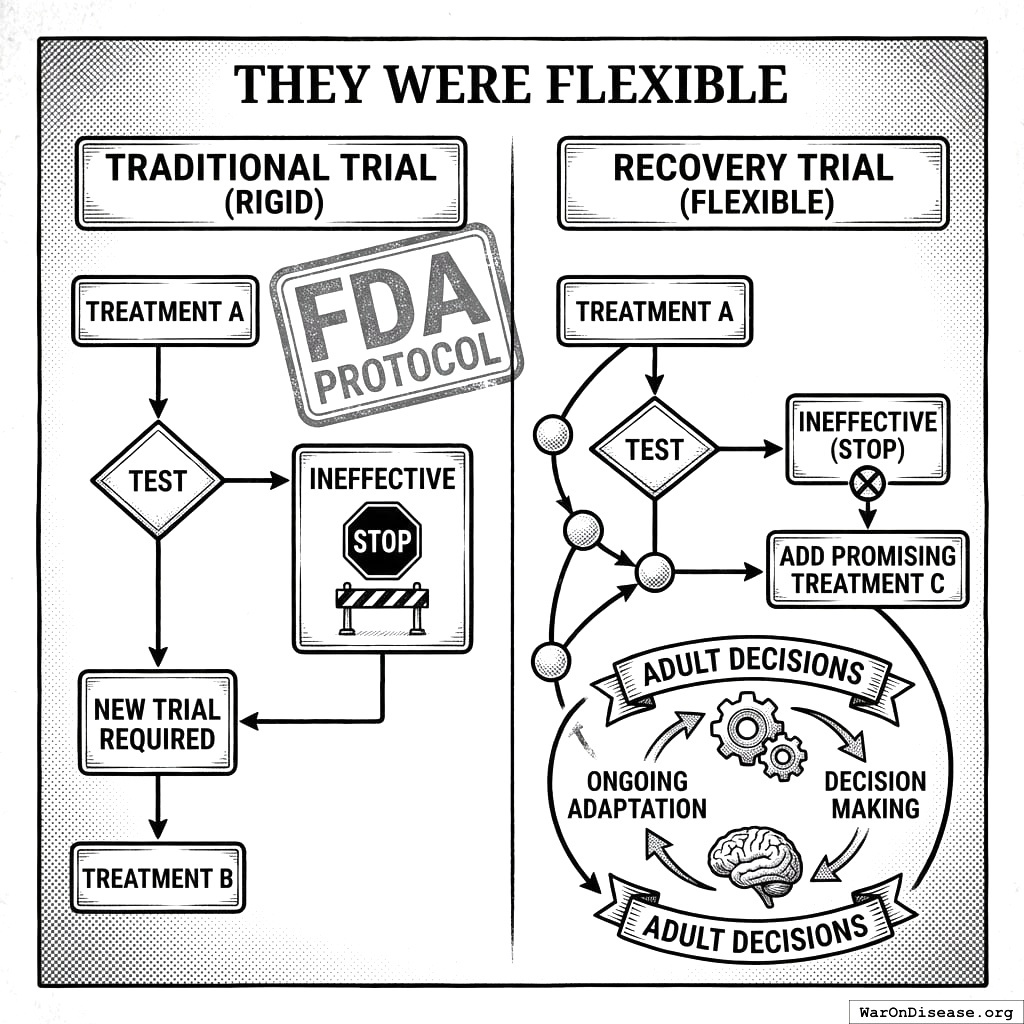
They Were Flexible
When a treatment didn’t work, they stopped testing it. When a new promising treatment emerged, they added it.
The FDA would require a completely new trial for each change. RECOVERY just… changed. Like adults making decisions.
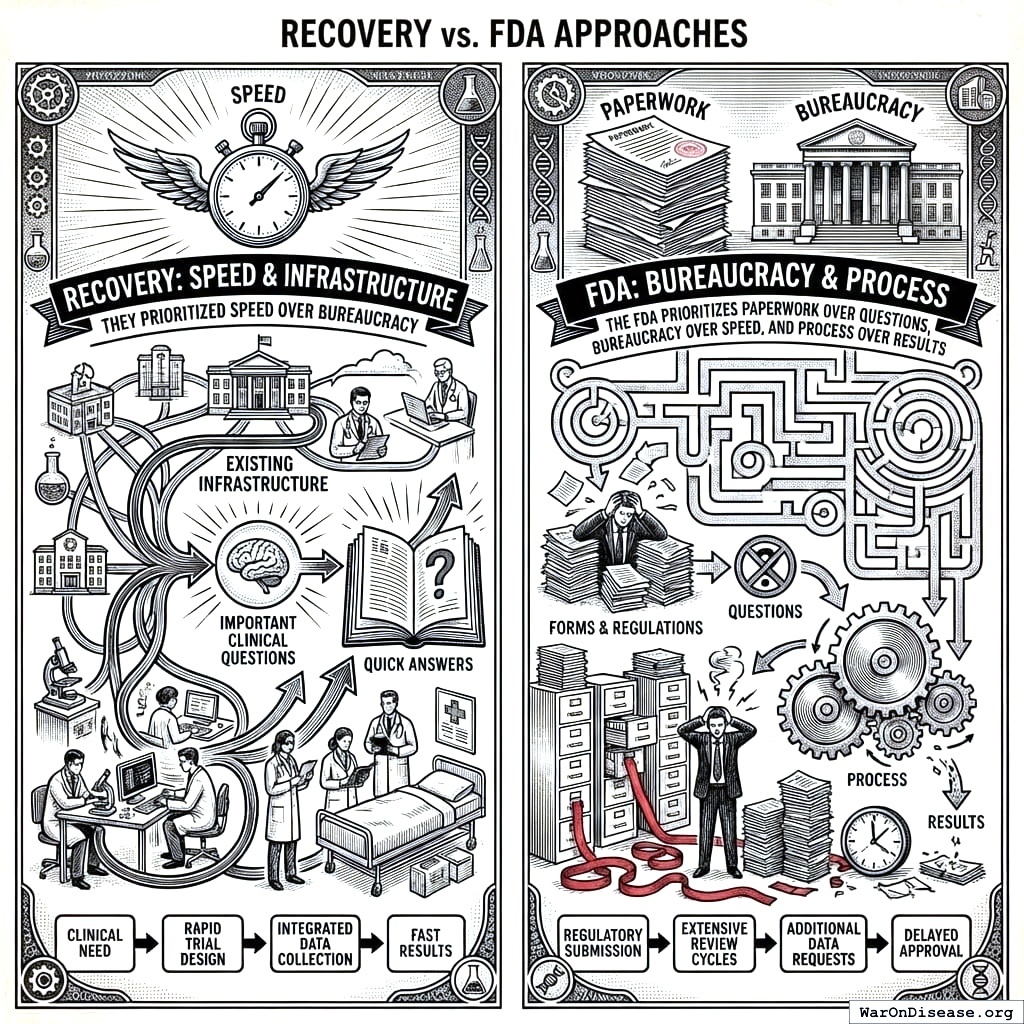
They Prioritized Speed Over Bureaucracy
RECOVERY answered important clinical questions quickly using existing infrastructure.
The FDA prioritizes paperwork over questions, bureaucracy over speed, and process over results.
What RECOVERY Proved
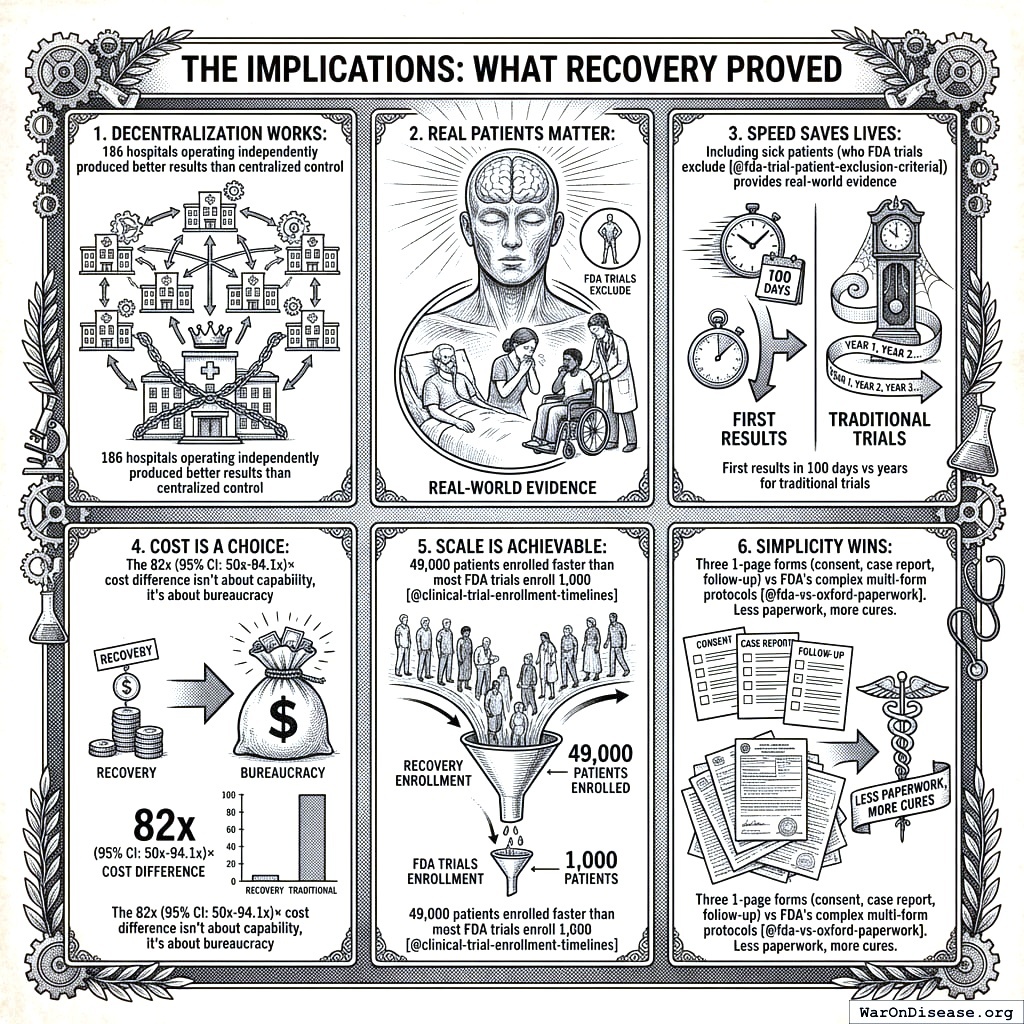
Six things RECOVERY proved:
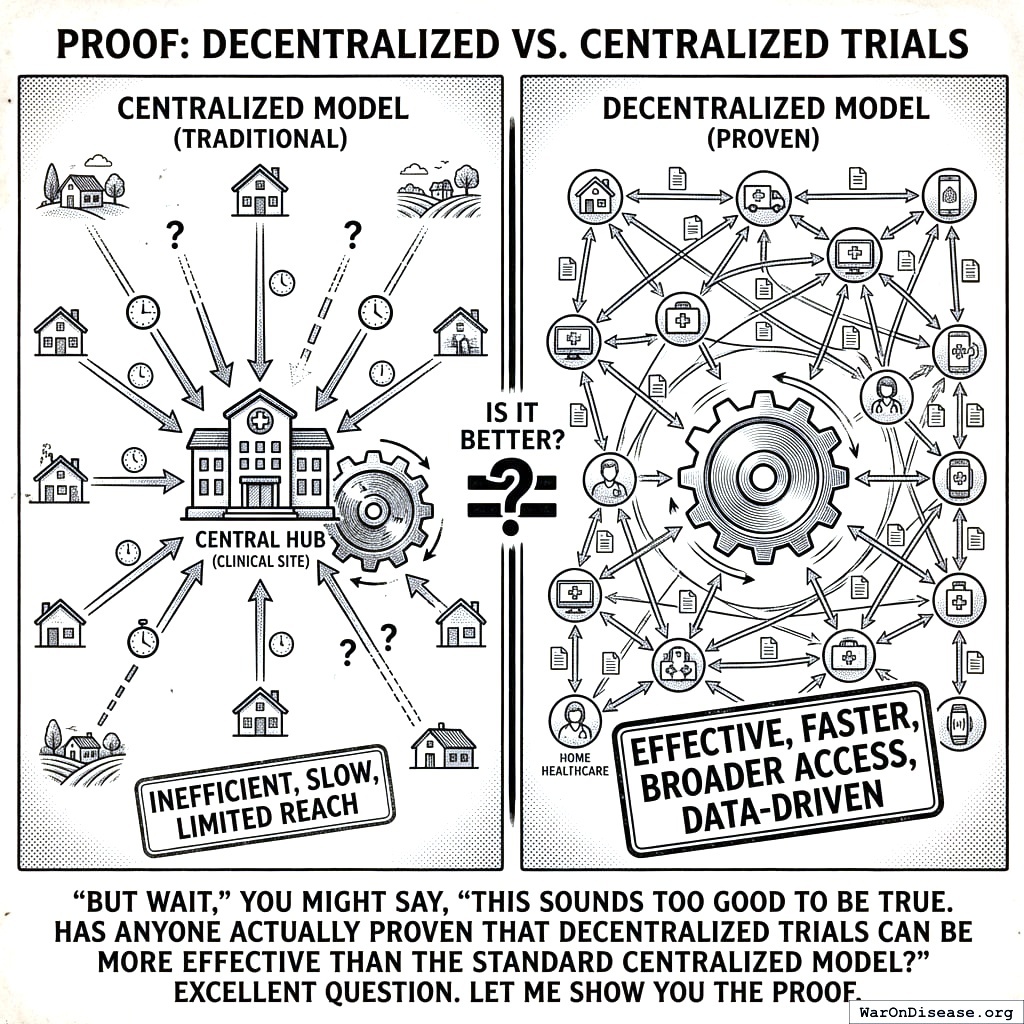
- Decentralization works. 186 hospitals. Better results than centralized control.
- Real patients matter. Traditional U.S. trials exclude the sickest people13. RECOVERY included them.
- Speed saves lives. 100 days to first result. Traditional: years.
- Cost is a choice. The 82x (90% CI: 21.4x-195x) gap is bureaucracy, not capability.
- Scale is achievable. 49,000 patients enrolled faster than most U.S. trials enroll 1,00014.
- Simplicity wins. Three 1-page forms vs. FDA’s multi-form protocols15.
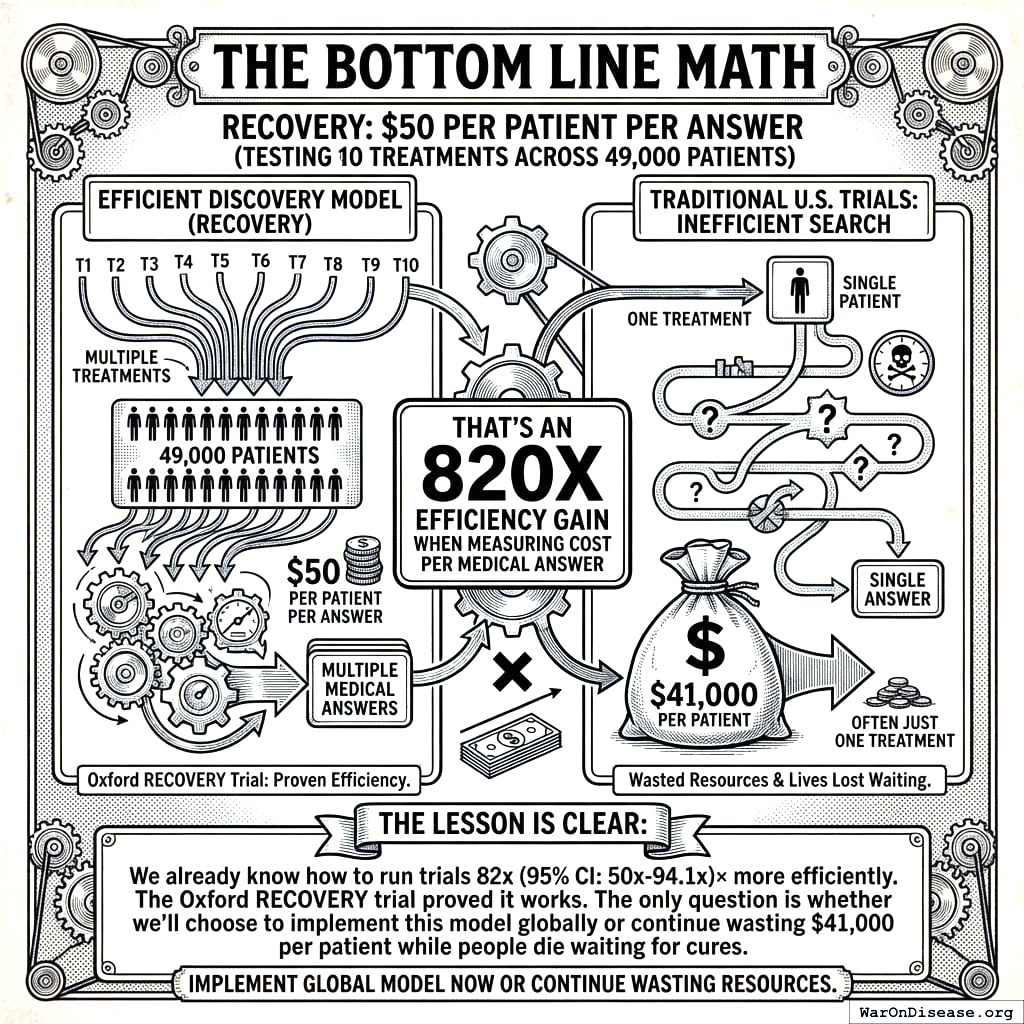
Cost Per Medical Answer
- RECOVERY: $50 per patient per answer (10 treatments, 49,000 patients)
- Traditional U.S. trials: $41,000 per patient, usually testing one treatment
- 820x efficiency gain per medical answer
You know how to do this 82x (90% CI: 21.4x-195x) more efficiently. Oxford proved it. The question is whether you scale it or keep spending $41,000 per patient while people die waiting.
Sources
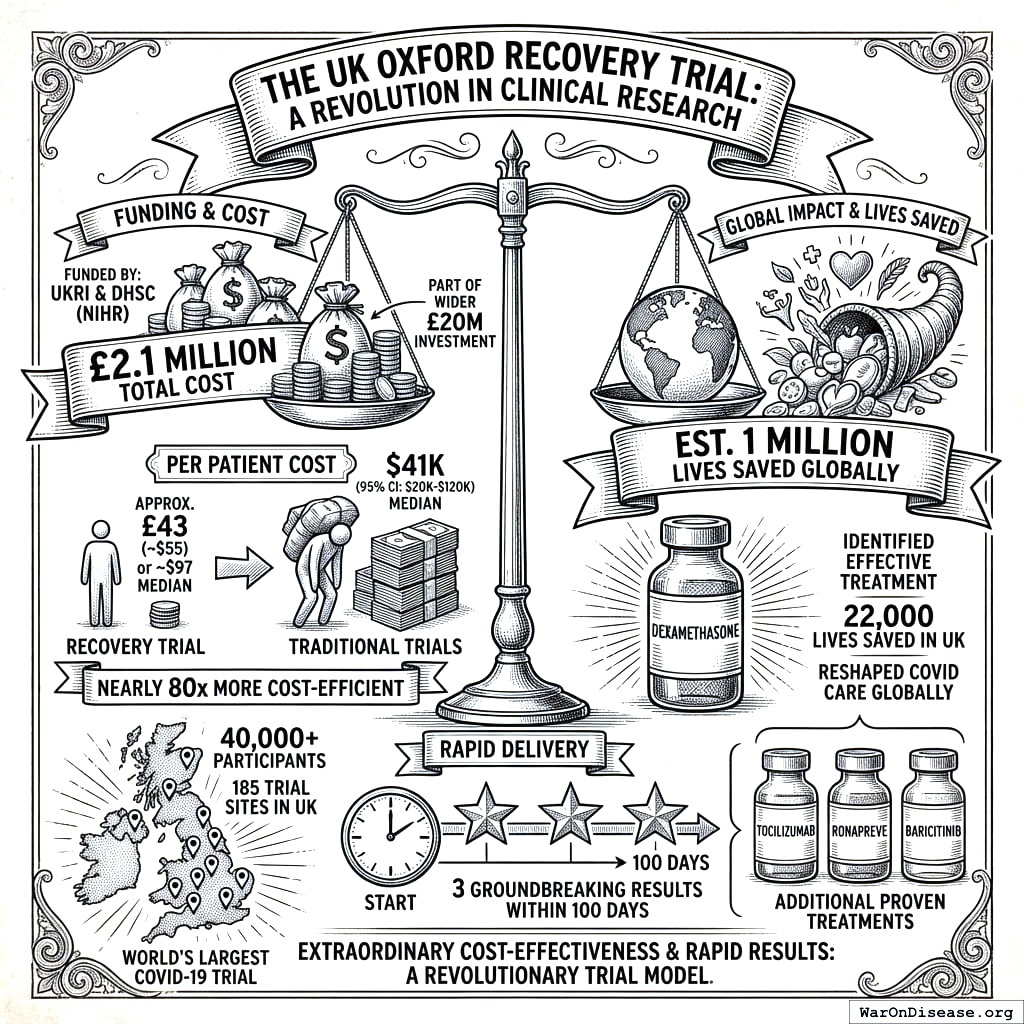
Cost: Total trial cost was £2.1M (~$2.7M). Funded jointly by UKRI and NIHR as part of a £20M rapid research response.8
Impact: Dexamethasone alone saved ~22,000 lives in the UK and 1 million globally by March 2021. Three groundbreaking results within 100 days. Four proven treatments total (dexamethasone, tocilizumab, Ronapreve, baricitinib). (UKRI8, Nuffield11)
Scale: 40,000+ participants across 185 sites. World’s largest COVID treatment trial.8
Cost per patient: Simple division gives ~£43 (~$55). Authoritative sources cite ~$500 (95% CI: $400-$2,500)9. A systematic review of 64 pragmatic trials found a median of $97 (95% CI: $19-$478)/patient16. Either way: nearly 82x (90% CI: 21.4x-195x) cheaper than traditional trials at $41,000 (95% CI: $20,000-$120,000)1.
Scaling RECOVERY’s Model
Apply RECOVERY’s approach to all drug development:
1.
Moore, T. J., Zhang, H., Anderson, G. & Alexander, G. C. Traditional trial cost per patient.
JAMA Internal Medicine https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7295430/ (2020)
The median cost of a pivotal trial was estimated to be $19 million... the median cost per patient was $41,413. Additional sources: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7295430/
.
2.
NHS England; Águas et al. RECOVERY trial global lives saved ( 1 million).
NHS England: 1 Million Lives Saved https://www.england.nhs.uk/2021/03/covid-treatment-developed-in-the-nhs-saves-a-million-lives/ (2021)
Dexamethasone saved 1 million lives worldwide (NHS England estimate, March 2021, 9 months after discovery). UK alone: 22,000 lives saved. Methodology: Águas et al. Nature Communications 2021 estimated 650,000 lives (range: 240,000-1,400,000) for July-December 2020 alone, based on RECOVERY trial mortality reductions (36% for ventilated, 18% for oxygen-only patients) applied to global COVID hospitalizations. June 2020 announcement: Dexamethasone reduced deaths by up to 1/3 (ventilated patients), 1/5 (oxygen patients). Impact immediate: Adopted into standard care globally within hours of announcement. Additional sources: https://www.england.nhs.uk/2021/03/covid-treatment-developed-in-the-nhs-saves-a-million-lives/ | https://www.nature.com/articles/s41467-021-21134-2 | https://pharmaceutical-journal.com/article/news/steroid-has-saved-the-lives-of-one-million-covid-19-patients-worldwide-figures-show | https://www.recoverytrial.net/news/recovery-trial-celebrates-two-year-anniversary-of-life-saving-dexamethasone-result
.
3.
Sir Martin Landray. Landray, sir martin, on the RECOVERY trial.
Sir Martin Landray https://www.ox.ac.uk/news/features/recovery-trial-two-years In 2019, I had no idea that I would be setting up a trial of treatments for an infectious disease, let alone a pandemic virus. I certainly would not have thought it possible to go from a blank piece of paper to enrolling the first patient in nine days, to finding the first life-saving treatment within ten weeks, and for it to be made standard NHS policy within three hours. Additional sources: https://www.ox.ac.uk/news/features/recovery-trial-two-years
.
4.
FDA. FDA clinical trial launch timeline.
FDA: IND Application Procedures https://www.fda.gov/drugs/investigational-new-drug-ind-application/ind-application-procedures-overview (2012)
IND application: FDA has 30 days to object or allow trials to begin NDA/BLA preparation after Phase 3: 6-12 months to assemble safety/effectiveness data Standard NDA review: 10-12 months median (standard review) Priority review: 6 months (vs 10 months standard) Overall development (first human testing to approval): 12-15 years full timeline Expedited programs: 7.1 years median vs 8.0 years nonexpedited Note: "6-12 months" likely refers to NDA/BLA preparation time post-Phase 3, not total trial launch timeline. IND review: 30 days. Full approval timeline: 10-15 years Additional sources: https://www.fda.gov/drugs/investigational-new-drug-ind-application/ind-application-procedures-overview | https://www.drugs.com/fda-approval-process.html | https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5820715/
.
6.
Drugs.com. FDA drug approval timeline.
Drugs.com: FDA Drug Approval Process https://www.drugs.com/fda-approval-process.html Full timeline (preclinical to market): 12-15 years average (10-15 years common range) Preclinical phase: 3-7 years Clinical development + NDA review: 9 years NDA review alone: 10 months average (standard); 6 months (priority review) Historical (pre-PDUFA): 21-29 months for NDA review Note: "10 years" is accurate for total development timeline (10-15 year range). Modern FDA review is faster (10 months) thanks to PDUFA, but overall timeline remains 12-15 years Additional sources: https://www.drugs.com/fda-approval-process.html | https://www.fdareview.org/issues/the-drug-development-and-approval-process/ | https://pmc.ncbi.nlm.nih.gov/articles/PMC6113340/
.
7.
RECOVERY Trial. RECOVERY trial cost reduction.
RECOVERY Trial https://www.recoverytrial.net/ Oxford RECOVERY trial achieved $500 per patient cost, compared to traditional Phase III trial costs of $40,000-120,000+ per patient. This represents an 80-100x+ cost reduction. Key strategies: embedding trial protocols within routine hospital care, minimizing overhead by leveraging existing staff/resources and electronic data capture, and focused pragmatic trial designs. Additional sources: https://www.recoverytrial.net/
.
9.
Professor Martin Landray (co-chief investigator), quoted in Oren Cass, Manhattan Institute. RECOVERY trial efficiency.
Professor Martin Landray (co-chief investigator) https://manhattan.institute/article/slow-costly-clinical-trials-drag-down-biomedical-breakthroughs (2023)
At a cost of $20 million for 48,000 patients, the RECOVERY trial cost about $500 per patient... that is about $50 per patient per answer. Additional sources: https://manhattan.institute/article/slow-costly-clinical-trials-drag-down-biomedical-breakthroughs
.
10.
RECOVERY Collaborative Group. RECOVERY trial cost-effectiveness ( $4/QALY, global impact methodology).
RECOVERY Trial Results https://www.recoverytrial.net/results RECOVERY trial (UK) cost $20M total and discovered that dexamethasone reduces COVID mortality by 1/3 in severe cases, saving 1 million lives globally. Using global impact methodology (research discovery value): $20M / (1M lives × 5 QALYs/life) = $4/QALY. This is 12,500× more cost-effective than standard NIH research allocation ($50,000/QALY). Additional sources: https://www.recoverytrial.net/results
.
13.
FDA. FDA trial patient exclusion criteria.
FDA: Evaluating Inclusion & Exclusion Criteria https://www.fda.gov/media/134754/download Most frequent exclusions: Pregnancy, lactation/breastfeeding, renal/hepatic abnormalities, specific infectious diseases Pregnant/lactating women: >90% of trials exclude Older adults: 27% exclude based on age (arbitrary upper limits) Patients with organ dysfunction: Excluded due to adverse impact concerns from comorbidities/concomitant meds Multiple chronic conditions: Often exclusion criterion despite being common in target population Children/adolescents: Excluded due to ethical considerations High-risk patients: Prior malignancy history, active brain metastases, suboptimal hepatic/renal function, HIV+ FDA guidance: Working to broaden eligibility; "exclusions based on age alone rarely appropriate Note: Exclusion criteria often eliminate patients who would actually use the drug, reducing real-world applicability of trial results Additional sources: https://www.fda.gov/media/134754/download | https://www.sciencedirect.com/science/article/abs/pii/S1551714421002512 | https://ascopubs.org/doi/10.1200/EDBK_155880
.
15.
PMC. Paperwork comparison between FDA trials and RECOVERY trial.
PMC: Making Trials Part of Good Clinical Care - RECOVERY https://pmc.ncbi.nlm.nih.gov/articles/PMC8285150/ RECOVERY trial paperwork: One-page consent form, one-page case report form, single follow-up form Randomisation form: Simple, collecting few baseline characteristics and ensuring eligibility Follow-up: Single form completed at earliest of discharge, death, or 28 days Eligibility criteria: Simple; trial processes (including paperwork) minimized Philosophy: "Avoid additional burden on busy clinicians, so trial procedures streamlined as far as possible FDA Form 1572: Statement of Investigator form required for IND trials (specific form, not total page count) Note: Specific "1,572 pages vs 24 pages" comparison not found in sources. RECOVERY used 1-page forms. FDA Form 1572 is a specific required form, not total paperwork count. RECOVERY’s streamlined approach demonstrated feasibility of simplified trial documentation Additional sources: https://pmc.ncbi.nlm.nih.gov/articles/PMC8285150/ | https://pmc.ncbi.nlm.nih.gov/articles/PMC9293394/ | https://www.fda.gov/media/71816/download
.
16.
Ramsberg, J. & Platt, R. Pragmatic trial cost per patient (median $97).
Learning Health Systems https://pmc.ncbi.nlm.nih.gov/articles/PMC6508852/ (2018)
Meta-analysis of 108 embedded pragmatic clinical trials (2006-2016). The median cost per patient was $97 (IQR $19–$478), based on 2015 dollars. 25% of trials cost <$19/patient; 10 trials exceeded $1,000/patient. U.S. studies median $187 vs non-U.S. median $27. Additional sources: https://pmc.ncbi.nlm.nih.gov/articles/PMC6508852/
.
17.
Tufts Center for Study of Drug Development. Post-1962 explosion in drug development costs.
Tufts Center for Study of Drug Development https://csdd.tufts.edu/cost-study (2014)
Cost to develop a new prescription drug: $2.6 billion (2014 Tufts study), increasing to $2.9 billion with post-approval development Represents 145% increase (inflation-adjusted) from 2003 estimate of $802 million Based on 106 drugs from 10 pharmaceutical companies tested between 1995-2007 Note: This study has been controversial; some organizations like Doctors Without Borders suggest actual costs may be substantially lower. Deloitte 2023 report shows costs continuing to rise Additional sources: https://csdd.tufts.edu/cost-study | https://cen.acs.org/articles/92/web/2014/11/Tufts-Study-Finds-Big-Rise.html
.
19.
FDA Study via NCBI. Trial costs, FDA study.
FDA Study via NCBI https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6248200/ Overall, the 138 clinical trials had an estimated median (IQR) cost of $19.0 million ($12.2 million-$33.1 million)... The clinical trials cost a median (IQR) of $41,117 ($31,802-$82,362) per patient. Additional sources: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6248200/
.