The Optimal Budget Generator: A Causal Inference Protocol for Maximizing Median Health and Wealth Through Public Goods Funding
Generating Integrated Public Budget Recommendations Using Diminishing Returns Modeling and Cost-Effectiveness Analysis

20-40% of public goods funding is misallocated relative to outcome-maximizing benchmarks, representing trillions annually in foregone welfare gains. Budget processes respond to lobbying intensity and historical precedent rather than causal evidence of effectiveness.
The Optimal Budget Generator (OBG) applies causal inference, diminishing returns modeling, and cost-effectiveness analysis to determine optimal public goods funding levels that maximize two terminal general-welfare metrics: real after-tax median income growth and median healthy life years. For each spending category, OBG estimates an Optimal Spending Level (OSL) identifying where marginal returns equal opportunity cost.
The Budget Impact Score (BIS) measures confidence in each OSL estimate based on study quality, statistical precision, and temporal recency of the underlying causal evidence. The result is a gap analysis showing which categories are over- or underfunded relative to evidence-based benchmarks, enabling systematic reallocation from low-return to high-return public investments. At system scale, the model’s Optimal Governance Trajectory reaches 56.7x (90% CI: 21x-148x) the Earth baseline after 20 years, raises average income to $1.16 million (90% CI: $429,664-$3.04 million) versus $20,483 on the status-quo path, reaches $10.7 quadrillion (90% CI: $3.95 quadrillion-$28 quadrillion) in total output, and recovers roughly $101 trillion (90% CI: $59.6 trillion-$161 trillion)/year in suppressed value (The Political Dysfunction Tax).
budget optimization, optimal budget generator, evidence-based policy, meta-analysis, cost-effectiveness, diminishing returns, cross-country analysis, public finance, welfare economics, spending targets
Abstract
Your government decides how much to spend on each category the same way it has for decades: last year’s number, plus whatever the loudest lobbyist got added, minus whatever the latest crisis forced a cut on. This is called “the budget process.” It has no optimization function. It has no feedback loop. It has no measurable objective. It is, in the technical sense, not a process at all. It is an accident that repeats annually.
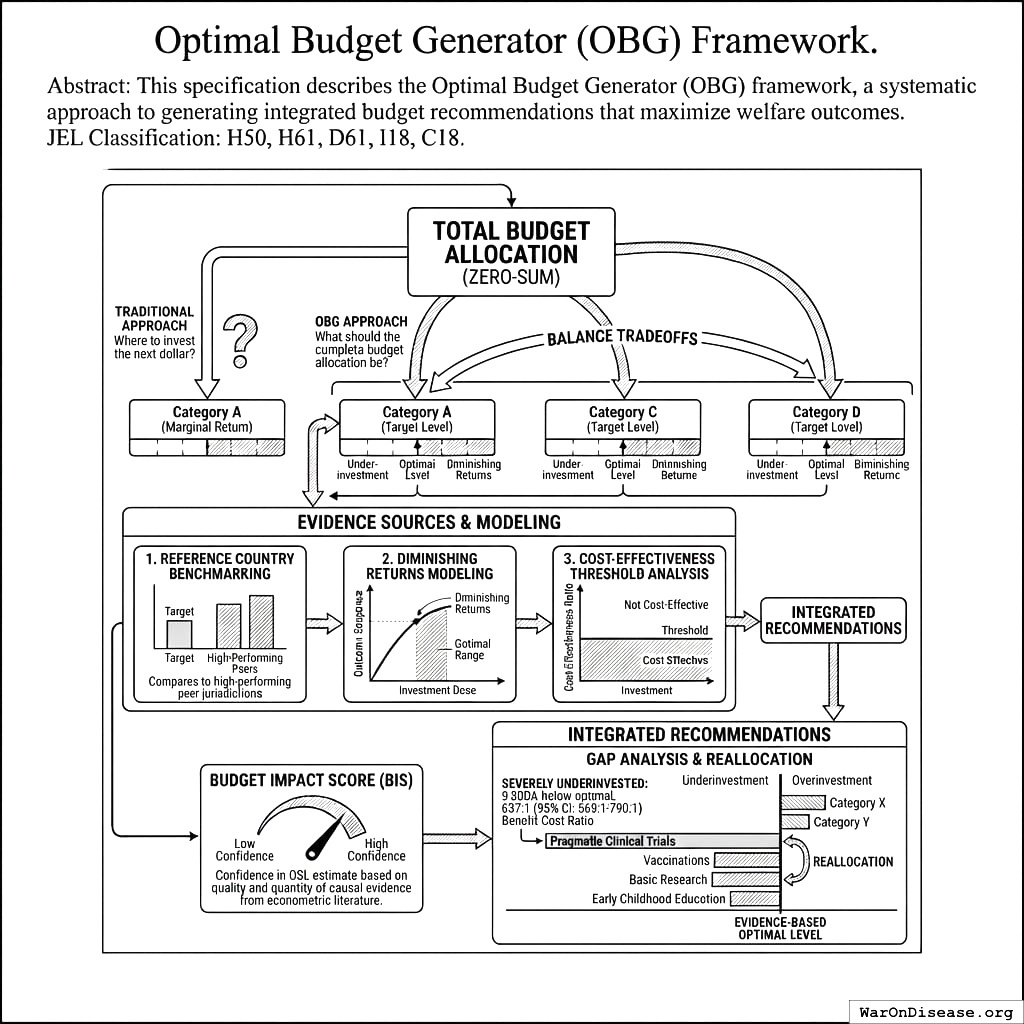
This specification describes the Optimal Budget Generator (OBG) framework, a systematic approach to generating integrated budget recommendations that maximize welfare as measured by two terminal general-welfare metrics: real after-tax median income growth and median healthy life years.
JEL Classification: H50, H61, D61, I18, C18
Unlike marginal-return frameworks that ask “where should we invest the next dollar?”, OBG asks “what should the complete budget allocation be?” Each category has a target level - too little means underinvestment, too much means diminishing returns. But unlike the Recommended Daily Allowance for nutrients (where you can meet all targets simultaneously), budget allocation is zero-sum: spending more on one category means less for others. OBG generates integrated recommendations that balance these tradeoffs.
The framework combines two evidence sources: (1) diminishing returns modeling from cross-country dose-response studies, and (2) cost-effectiveness threshold analysis from health economics. The Budget Impact Score (BIS) measures our confidence in each category’s OSL estimate based on the quality and quantity of causal evidence from the econometric literature.
The result is a gap analysis showing which categories are below evidence-based optimal levels, enabling systematic reallocation from overinvestment to underinvestment. Applied to the US federal budget, the framework identifies pragmatic clinical trials as the most severely underinvested category (9,900% below optimal with 439 (90% CI: 321-600):1 benefit-cost ratio), followed by vaccinations, outcome-funded R&D, and early childhood education.
Scale note. If budget allocation is the core bottleneck, the upside from fixing it is civilization-scale. Under the project’s best-case governance ceiling, the recoverable upside is $101 trillion (90% CI: $59.6 trillion-$161 trillion) per year. Over 20 years, the Optimal Governance Trajectory reaches 56.7x (90% CI: 21x-148x) the Earth baseline, raises average income to $1.16 million (90% CI: $429,664-$3.04 million) versus $20,483 on the status-quo path, and reaches $10.7 quadrillion (90% CI: $3.95 quadrillion-$28 quadrillion) in total output. This specification focuses on the allocation layer of that plan; the full derivation lives in The Political Dysfunction Tax1.
System Overview
What Policymakers See
A dashboard showing spending gaps by category, with clear recommendations:
Illustrative Example: US Federal Budget Gap Analysis
The following table demonstrates how OBG output would appear. OSL estimates for fully derived categories (pragmatic trials, vaccinations) come from the worked examples in Sections 6-7. Remaining OSL estimates use cross-country benchmarking.
| Category | Current | OSL | Gap | Evidence | Income Effect | Health Effect | Action |
|---|---|---|---|---|---|---|---|
| Pragmatic clinical trials | $0.5B | $50B | +$49.5B | A (RCTs) | ++ | +++ | Scale 100x |
| Vaccinations | $8B | $35B | +$27B | A (RCTs) | + | +++ | Increase |
| Basic research | $45B | $90B | +$45B | B (spillovers) | ++ | ++ | Increase |
| Early childhood (0-5) | $50B | $70B | +$20B | A (RCTs) | +++ | + | Increase |
| Military (discretionary) | $850B | $459B | -$391B | C (benchmarks) | − | − | Decrease |
| Agricultural subsidies | $25B | $0B | -$25B | A (welfare analysis) | − | − | Eliminate |
Positive gaps indicate underinvestment; negative gaps indicate overinvestment. Income Effect: impact on real after-tax median income growth. Health Effect: impact on median healthy life years. Scale: +++ strong positive, ++ moderate positive, + weak positive, − negative.
What Budget Analysts See
- OSL estimates with confidence intervals and methodology notes
- Cross-country spending data showing spending-outcome relationships
- Diminishing returns curves identifying optimal spending levels
- Evidence quality scores (BIS) for each category
- Sensitivity analysis showing how OSL changes with different assumptions
- Priority rankings by gap size weighted by evidence confidence
Where This Fits
+-------------------------------------------------------------+
|                    OPTIMOCRACY FRAMEWORK                     |
+-------------------------------------------------------------+
|                                                              |
|  +---------------------+    +-----------------------------+  |
|  |  Budget Generator   |    |  Policy Generator           |  |
|  |  (OBG/BIS Framework)|    |  (OPG/PIS Framework)        |  |
|  |                     |    |                             |  |
|  |  Answers:           |    |  Answers:                   |  |
|  |  "How should we     |    |  "What policies should      |  |
|  |  allocate the       |    |  we adopt/change?"          |  |
|  |  budget?"           |    |                             |  |
|  |                     |    |                             |  |
|  |  Primary output:    |    |  Primary output:            |  |
|  |  Integrated budget  |    |  Enact/Replace/Repeal       |  |
|  |  recommendations    |    |  recommendations            |  |
|  +---------------------+    +-----------------------------+  |
|                                                              |
|  Both feed into: Constitutional Layer (outcome-optimizing rules)  |
+-------------------------------------------------------------+
The OBG/BIS framework answers: “Given what we know about returns to spending, what are the optimal allocation levels?”
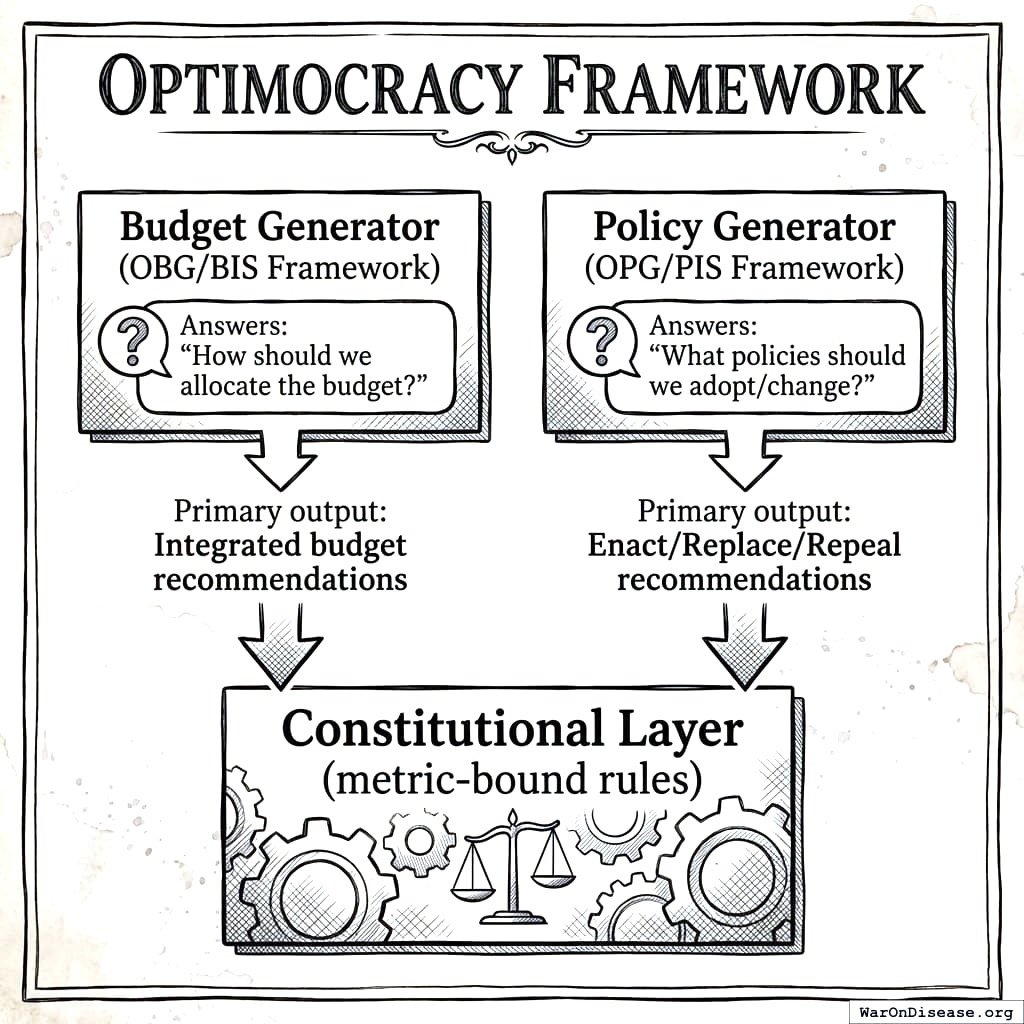
The OPG framework (see Optimal Policy Generator Specification2) answers: “Which policy reforms beyond budget allocation would most improve welfare?”
Implementation Mechanism
This specification focuses on generating evidence-based budget recommendations. Political implementation mechanisms are discussed separately in Incentive Alignment Bonds3.
Introduction
Why Budget Allocation Fails Today
Budget allocation is fundamentally a problem of social choice under uncertainty4. The challenge is not simply technical but institutional: current budget processes systematically diverge from welfare-optimal allocations due to political economy dynamics5,6.
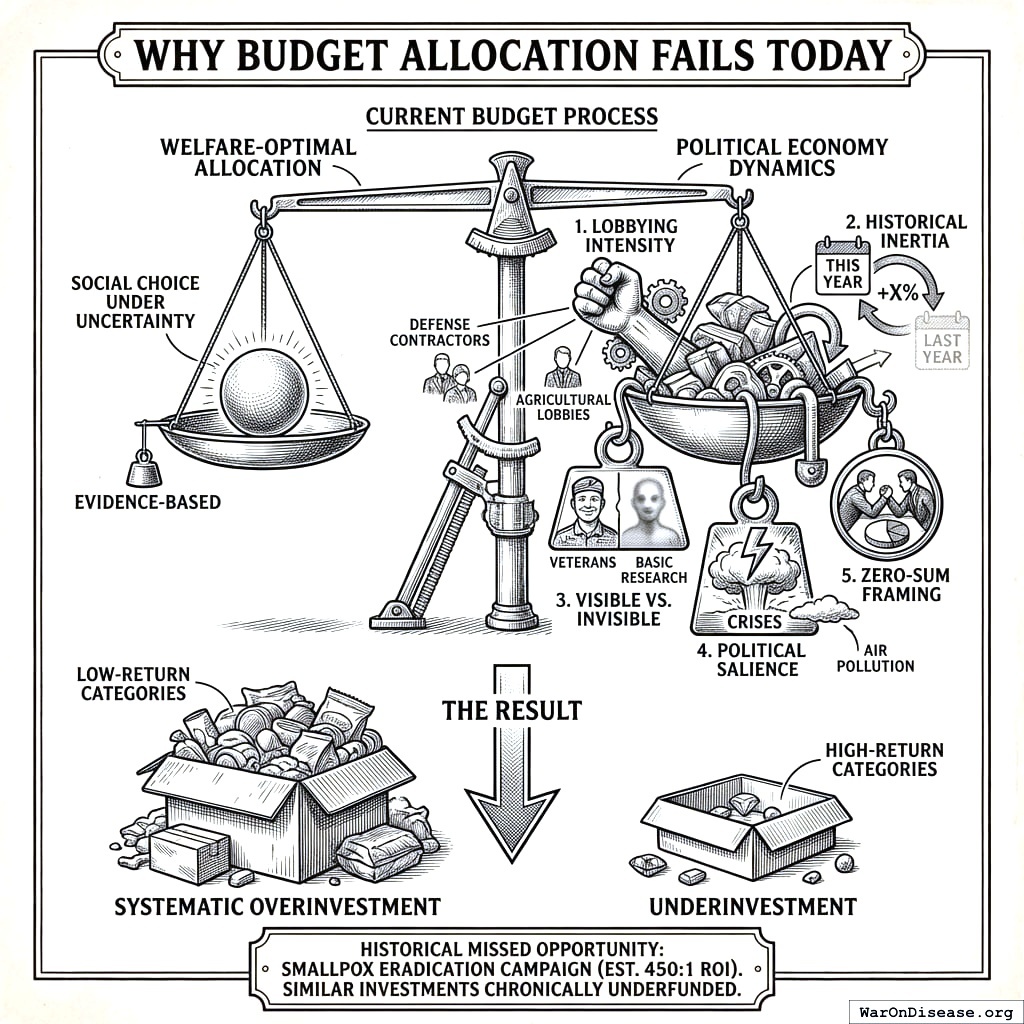
Current budget allocation follows a process dominated by:
- Lobbying intensity: Categories with organized beneficiaries (weapons manufacturers, agricultural lobbies) receive disproportionate funding regardless of evidence
- Historical inertia: This year’s budget is last year’s budget plus a percentage, not a fresh optimization
- Visible vs. invisible beneficiaries: Programs with identifiable beneficiaries (veterans) outcompete programs with diffuse beneficiaries (clinical trials, vaccinations)
- Political salience: Crises drive spending regardless of cost-effectiveness (terrorism vs. air pollution)
- Zero-sum framing: Budget debates treat all categories as competing rather than asking which ones are at optimal levels
The result: systematic overinvestment in low-return categories and underinvestment in high-return categories. Historical examples demonstrate the scale of missed opportunities: the smallpox eradication campaign returned an estimated 450:1 ROI7, yet similar high-return public health investments remain chronically underfunded.
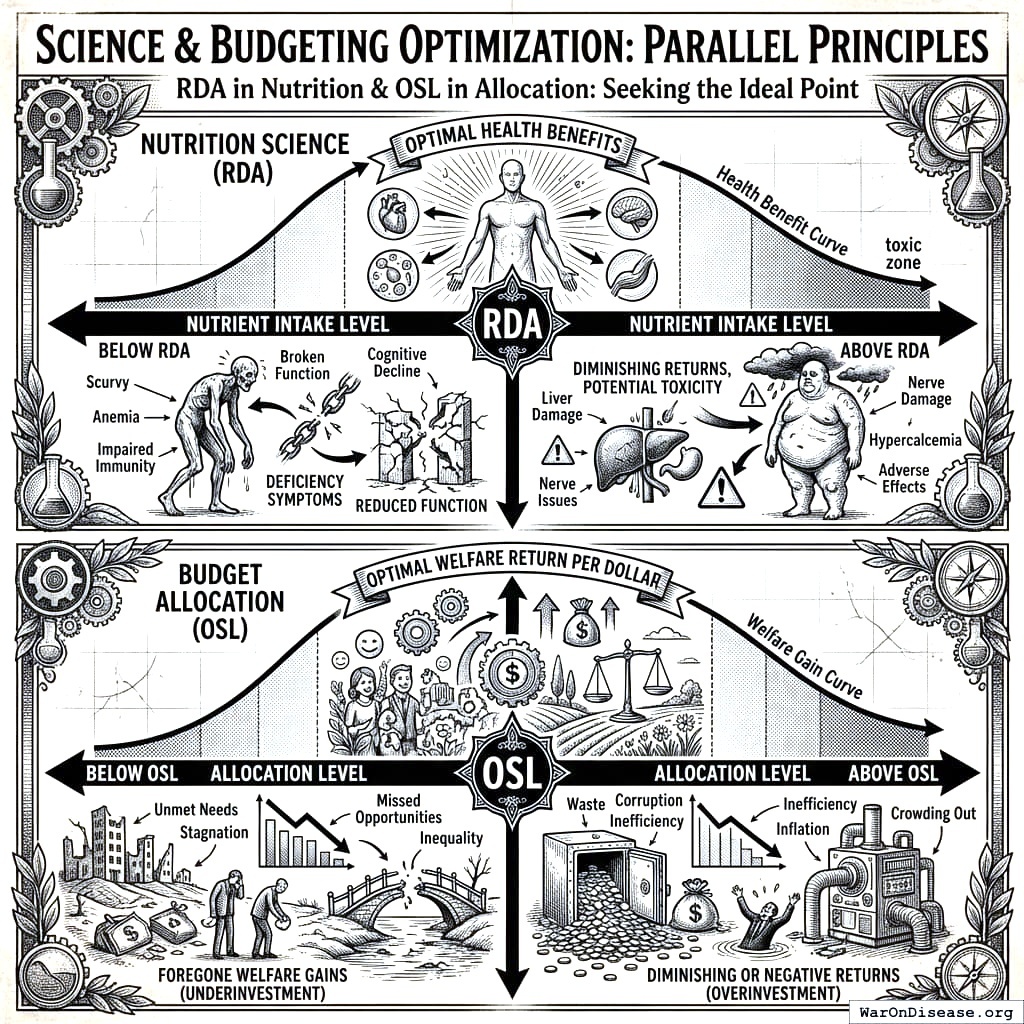
The RDA Analogy: Optimal Levels, Not Just Marginal Returns
Nutrition science doesn’t just say “eat more vitamins.” It specifies Recommended Daily Allowances - target intake levels where:
- Below RDA: Deficiency symptoms, reduced function
- At RDA: Optimal health benefits
- Above RDA: Diminishing returns, potential toxicity
Budget allocation should work the same way. For each spending category:
- Below OSL: Foregone welfare gains (underinvestment)
- At OSL: Optimal welfare return per dollar
- Above OSL: Diminishing or negative returns (overinvestment)
infinite spending on any category doesn’t make sense, even one with high returns. Early childhood education has excellent returns - but spending $10 trillion on it wouldn’t produce 10x the benefits of spending $1 trillion. There’s an optimal level.
What This Framework Provides
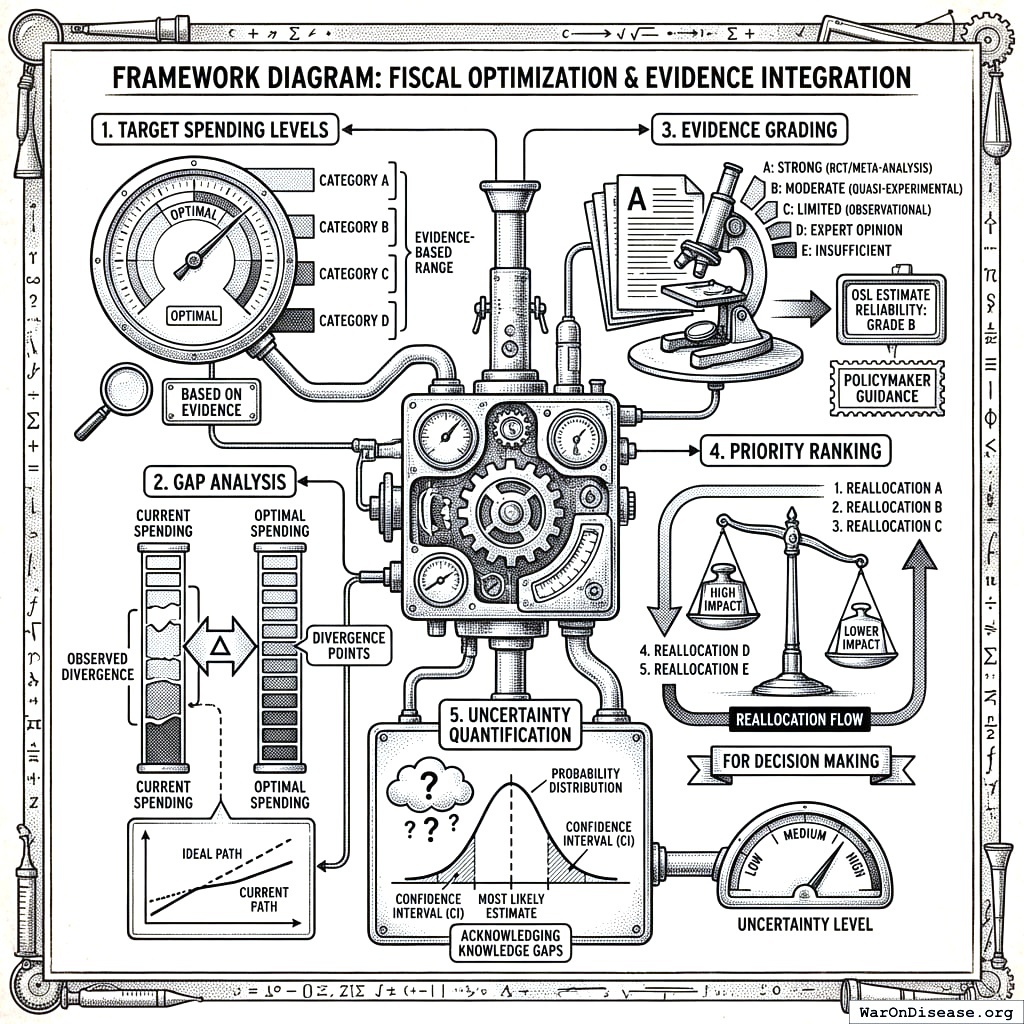
- Target spending levels for each budget category based on evidence
- Gap analysis showing where current spending diverges from optimal
- Evidence grading so policymakers know which OSL estimates are reliable
- Priority ranking for reallocation decisions
- Uncertainty quantification around each estimate
Outcome Metrics: What We’re Optimizing
All OBG recommendations ultimately aim to maximize two terminal general-welfare metrics:
Real after-tax median income growth (pp/year): Year-over-year percentage change in inflation-adjusted, post-tax median household income. Sources: Census Bureau, BLS.
Median healthy life years (years): Expected years of life in good health at the population median. Sources: WHO Global Health Observatory, national health surveys.
The welfare function combines these with equal weight by default:
\[ W = 0.5 \cdot \text{IncomeGrowth} + 0.5 \cdot \text{HealthyYears} \]
Why these two metrics? They are the terminal general-welfare metrics: the best currently measurable civilization-scale endpoints for approximating the terminal values defined in What Matters, pleasant consciousness and unpleasant consciousness. Most policy effects eventually show up in one or both. Economic policies (taxes, regulations, trade) primarily affect income growth. Health policies (healthcare access, public health, safety) primarily affect healthy life years. Education and infrastructure affect both. See Two-Metric Welfare Function for the complete framework.
Every spending category’s OSL is ultimately justified by its expected impact on these two metrics. The gap analysis and priority rankings reflect which reallocations would most improve the combined welfare function.
Related Work
The OBG framework builds on and extends several established traditions in public finance and evidence-based policy.
Budget Analysis Frameworks
Congressional Budget Office (CBO) Scoring. The CBO provides cost estimates for proposed legislation, projecting fiscal impacts over 10-year windows8. However, CBO scoring focuses on cost rather than welfare optimization - it answers “what will this cost?” not “what should we spend?” OBG complements CBO analysis by providing evidence-based spending targets against which proposals can be evaluated.
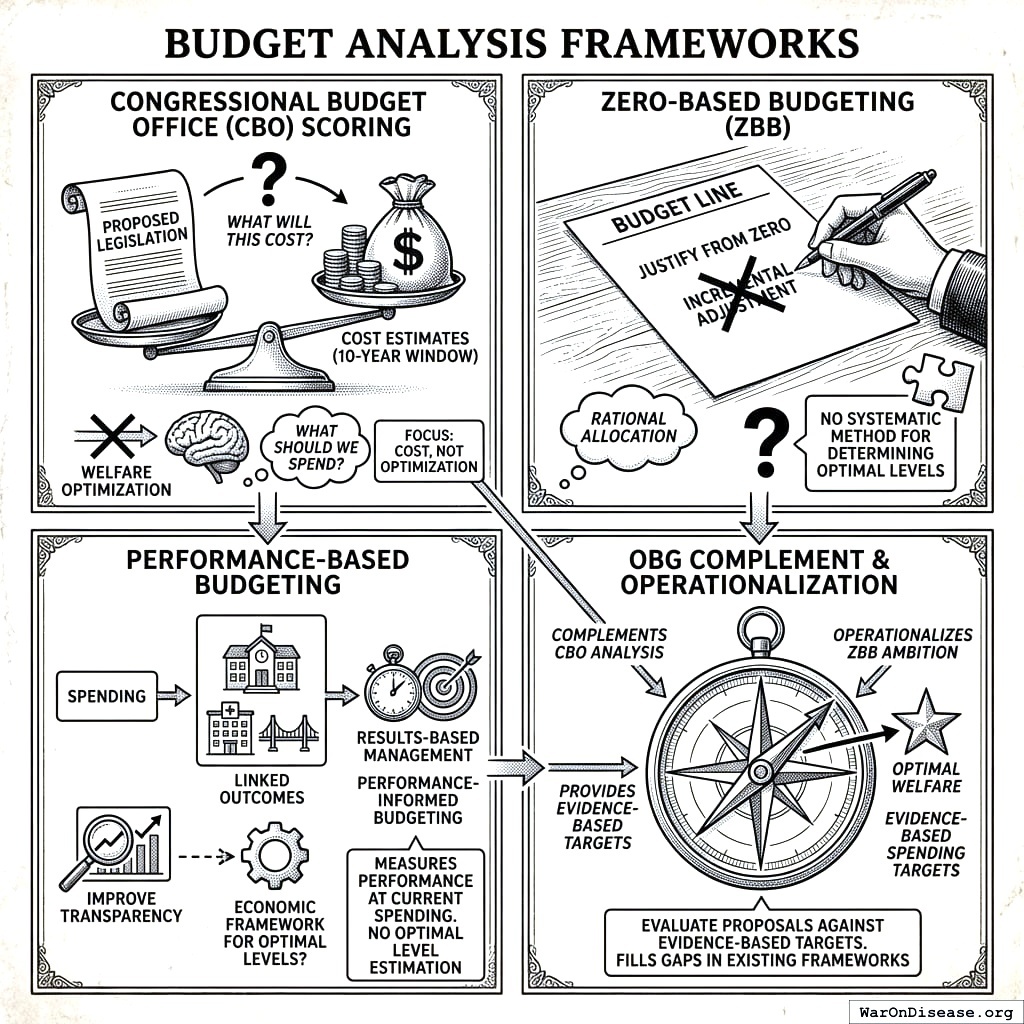
Performance-Based Budgeting. Since the Planning-Programming-Budgeting System (PPBS) of the 1960s, governments have attempted to link spending to outcomes. Modern variants include Results-Based Management and Performance-Informed Budgeting. These approaches improve transparency but typically lack the economic framework for determining optimal levels - they measure performance at current spending without estimating what spending should be.
Zero-Based Budgeting. ZBB requires justifying each budget line from zero rather than incremental adjustment. While philosophically aligned with OBG’s goal of rational allocation, ZBB provides no systematic method for determining optimal levels. OBG operationalizes ZBB’s ambition with evidence-based targets.
Evidence-Based Policy Movement
What Works Clearinghouses. Organizations like the What Works Clearinghouse (education), Cochrane Collaboration (health), and Campbell Collaboration (social policy) synthesize intervention evidence through systematic reviews. OBG draws on these evidence bases but extends beyond intervention evaluation to budget-level optimization. While clearinghouses answer “does this work?”, OBG answers “how much should we spend?”
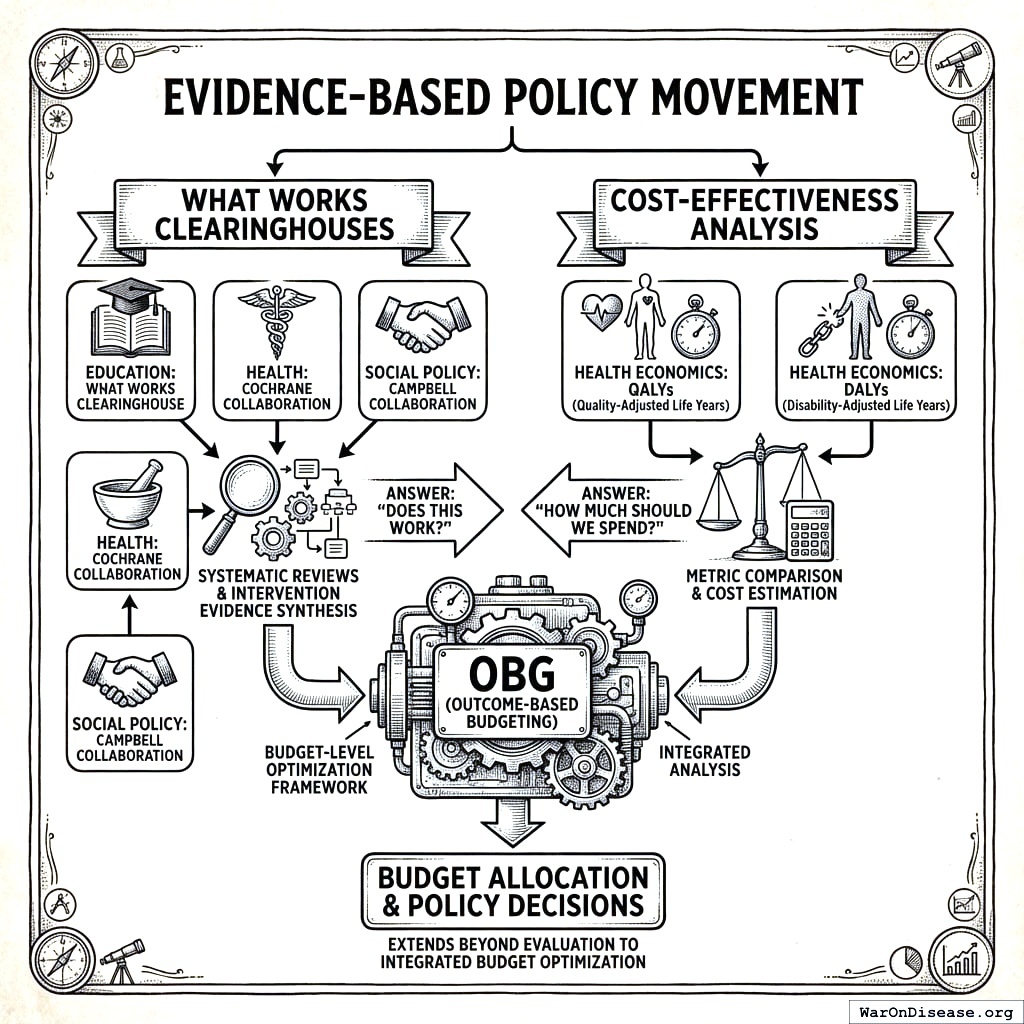
Cost-Effectiveness Analysis. Health economics has developed methods for comparing interventions using metrics like QALYs (Quality-Adjusted Life Years) and DALYs (Disability-Adjusted Life Years)9. OBG incorporates cost-effectiveness as one of two estimation methods but applies it within an integrated budget optimization framework rather than intervention-by-intervention.
Comparative Public Finance
OECD Government Spending Analysis. The OECD publishes extensive cross-country spending comparisons and outcome data10,11. OBG leverages this data infrastructure for diminishing returns analysis while adding the conceptual framework of optimal levels and evidence-weighted confidence.
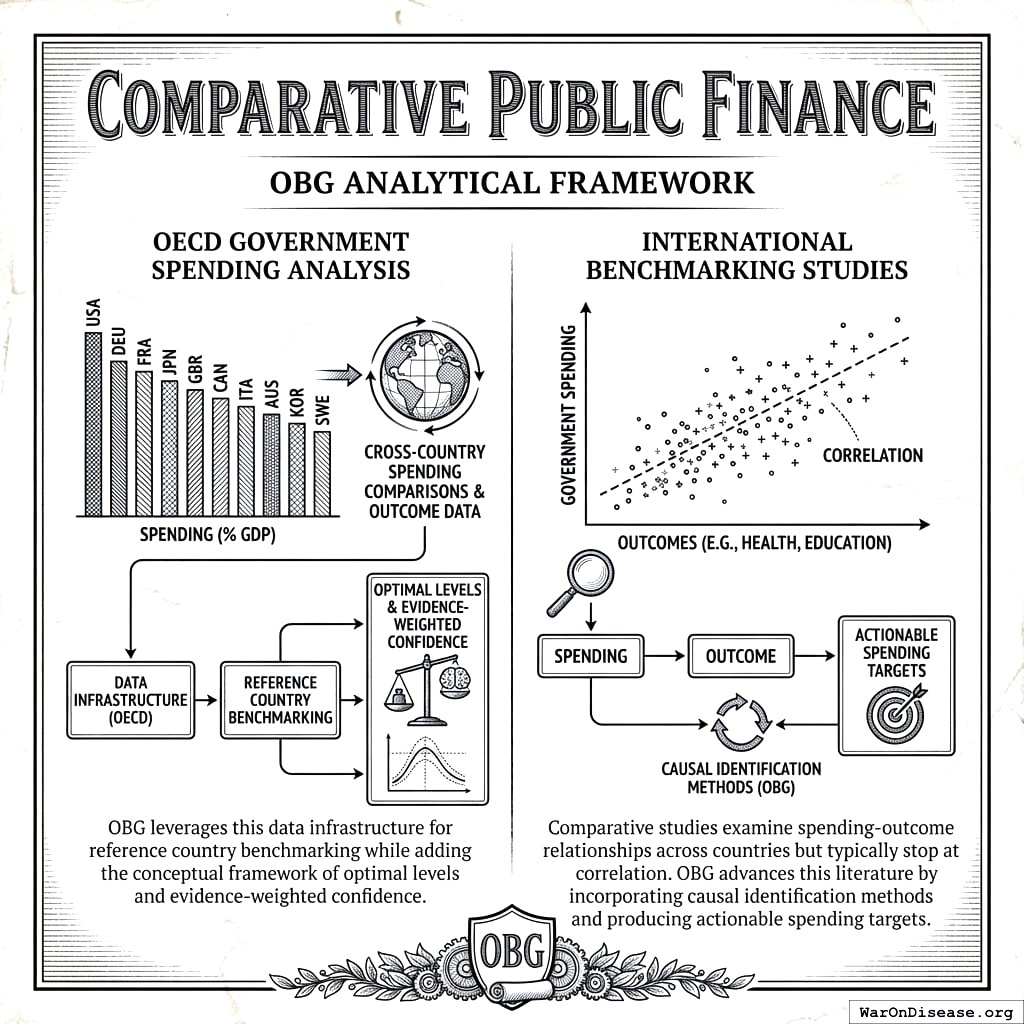
International Benchmarking Studies. Comparative studies examine spending-outcome relationships across countries but typically stop at correlation. OBG advances this literature by incorporating causal identification methods and producing actionable spending targets.
How OBG Differs
The OBG framework advances existing approaches in three key ways:
- Integrated multi-method estimation. Rather than relying on a single approach, OBG combines OSL estimates from diminishing returns modeling and cost-effectiveness analysis. This provides robustness and identifies where methods agree or conflict.
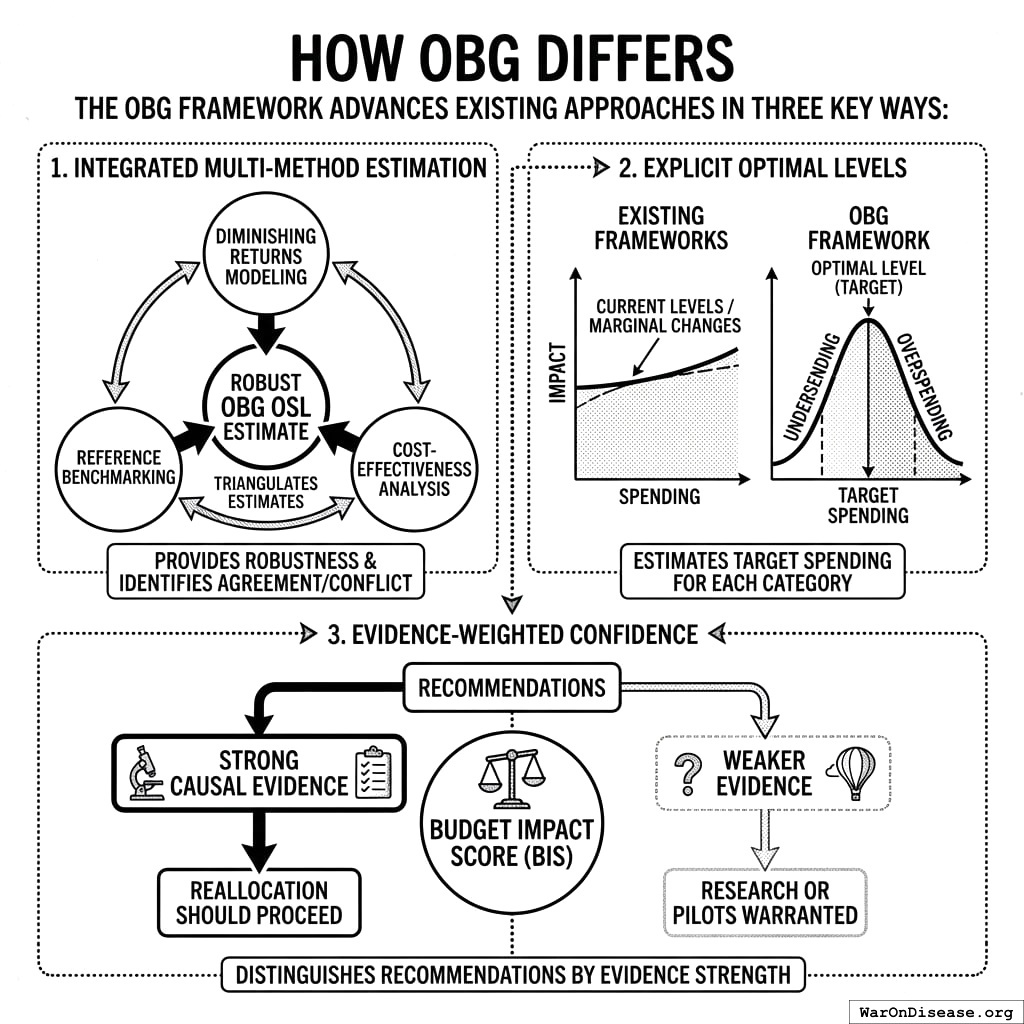
Explicit optimal levels. Unlike frameworks that analyze spending at current levels or propose marginal changes, OBG estimates target spending levels for each category - acknowledging that both underspending and overspending are suboptimal.
Evidence-weighted confidence. The Budget Impact Score (BIS) distinguishes recommendations supported by strong causal evidence (where reallocation should proceed) from those based on weaker evidence (where research or pilots are warranted).
Theoretical Framework
This section formalizes the OBG framework as a social planner’s optimization problem, establishing the theoretical foundations for optimal spending levels and evidence-weighted allocation.
Optimal Spending Levels Under Uncertainty
In practice, the welfare functions \(W_i(\cdot)\) are not known with certainty. Let \(\hat{W}_i(s)\) denote the planner’s estimate of welfare, with associated uncertainty \(\sigma_i^2(s)\).
Definition 1 (Optimal Spending Level). The Optimal Spending Level for category \(i\) is:
\[ \text{OSL}_i \equiv \arg\max_{s_i} \mathbb{E}[\hat{W}_i(s_i)] - \frac{\rho}{2} \text{Var}[\hat{W}_i(s_i)] \]
where \(\rho \geq 0\) is the planner’s risk aversion parameter.
For risk-neutral planners (\(\rho = 0\)), OSL reduces to the spending level that maximizes expected welfare. For risk-averse planners, OSL accounts for estimation uncertainty.
Proposition 2 (OSL Characterization). Under Assumption 1, with estimated marginal welfare \(\hat{W}_i'(s)\) and estimation variance \(\sigma_i^2(s)\), the OSL satisfies:
\[ \mathbb{E}[\hat{W}_i'(\text{OSL}_i)] = r + \rho \cdot \frac{\partial \sigma_i^2}{\partial s}\bigg|_{s=\text{OSL}_i} \]
where \(r\) is the social discount rate (opportunity cost of public funds).
Proof. The first-order condition for the uncertainty-adjusted maximization problem yields the result. The term \(r\) represents the marginal value of funds in alternative uses; the second term adjusts for risk. \(\square\)
Budget Impact Score as Precision Weighting
The Budget Impact Score formalizes the precision of OSL estimates, enabling evidence-weighted reallocation decisions.
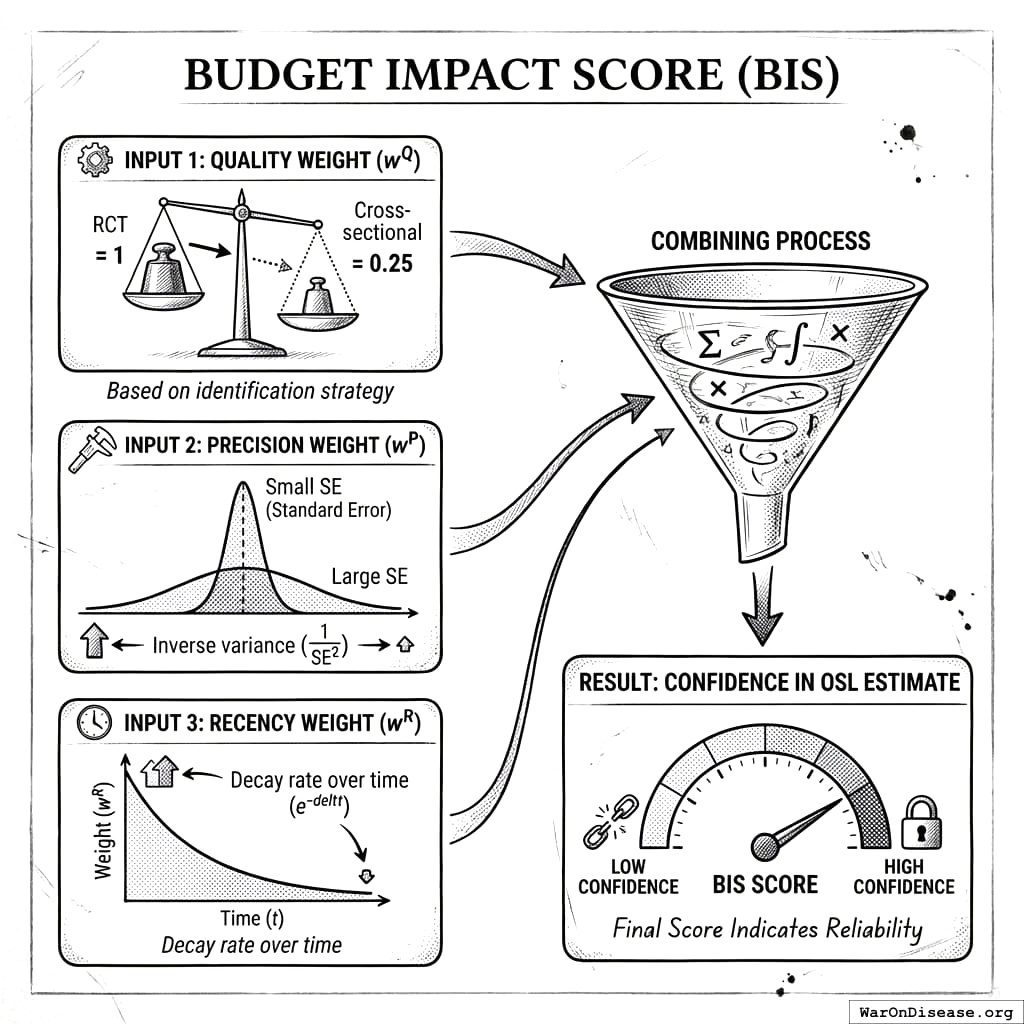
Definition 2 (Budget Impact Score). For category \(i\) with \(n_i\) effect estimates \(\{\hat{\beta}_{ij}\}_{j=1}^{n_i}\), the Budget Impact Score is:
\[ \text{BIS}_i = \min\left(1, \frac{1}{K} \sum_{j=1}^{n_i} w_j^Q \cdot w_j^P \cdot w_j^R \right) \]
where:
- \(w_j^Q \in (0,1]\) = quality weight based on identification strategy (RCT = 1, cross-sectional = 0.25)
- \(w_j^P = 1/\text{SE}(\hat{\beta}_j)^2\) = precision weight (inverse variance)
- \(w_j^R = e^{-\delta(t_{now} - t_j)}\) = recency weight with decay rate \(\delta\)
- \(K\) = calibration constant
Proposition 3 (BIS as Inverse Variance). Under standard meta-analytic assumptions, BIS is proportional to the precision of the pooled effect estimate:
\[ \text{BIS}_i \propto \frac{1}{\text{Var}(\hat{\beta}_i^{pooled})} \]
where \(\hat{\beta}_i^{pooled}\) is the quality-weighted pooled estimate of spending effects.
Gap Analysis and Welfare Gains
Definition 3 (Spending Gap). The spending gap for category \(i\) is:
\[ \text{Gap}_i = \text{OSL}_i - s_i^{current} \]
Proposition 4 (Welfare Gains from Gap Closure). For small gaps, the welfare gain from moving spending from current level to OSL is approximately:
\[ \Delta W_i \approx W_i'(s_i^{current}) \cdot \text{Gap}_i - \frac{1}{2} |W_i''(\bar{s})| \cdot \text{Gap}_i^2 \]
where \(\bar{s}\) is between \(s_i^{current}\) and \(\text{OSL}_i\).
Proof. Taylor expansion of \(W_i(\text{OSL}_i) - W_i(s_i^{current})\) around \(s_i^{current}\). \(\square\)
Corollary 1 (Priority Ranking). Categories should be prioritized for reallocation in order of:
\[ \text{Priority}_i = |\text{Gap}_i| \times \text{BIS}_i \times |W_i'(s_i^{current})| \]
This ranks categories by expected welfare gain adjusted for estimation confidence.
Note: In the simplified implementation (Section 10.2), we normalize by setting \(|W_i'(s_i^{current})| = 1\) for all categories, reducing the priority formula to \(\text{Priority}_i = |\text{Gap}_i| \times \text{BIS}_i\). This assumes equal marginal welfare weights across categories as a first approximation. Future iterations could incorporate category-specific marginal welfare estimates.
Welfare Bounds Under Model Uncertainty
When the functional form of \(W_i(\cdot)\) is uncertain, we can establish bounds on welfare gains.
Proposition 5 (Welfare Bounds). Let \(\underline{W}_i\) and \(\overline{W}_i\) denote lower and upper bounds on the welfare function consistent with available evidence. Then:
\[ \underline{\Delta W} = \sum_{i: \text{Gap}_i > 0} \underline{W}_i'(s_i) \cdot \text{Gap}_i \leq \Delta W \leq \sum_{i: \text{Gap}_i > 0} \overline{W}_i'(s_i) \cdot \text{Gap}_i = \overline{\Delta W} \]
The OBG framework reports both point estimates and these bounds via sensitivity analysis.
Summary of Theoretical Results
| Result | Implication for OBG |
|---|---|
| Proposition 1 | Optimal allocation equalizes marginal returns |
| Proposition 2 | OSL accounts for both expected returns and uncertainty |
| Proposition 3 | BIS captures estimation precision |
| Proposition 4 | Gap closure yields quantifiable welfare gains |
| Corollary 1 | Priority ranking optimizes reallocation sequence |
| Proposition 5 | Welfare bounds enable robust recommendations |
Core Methodology
Spending Category Data Structure
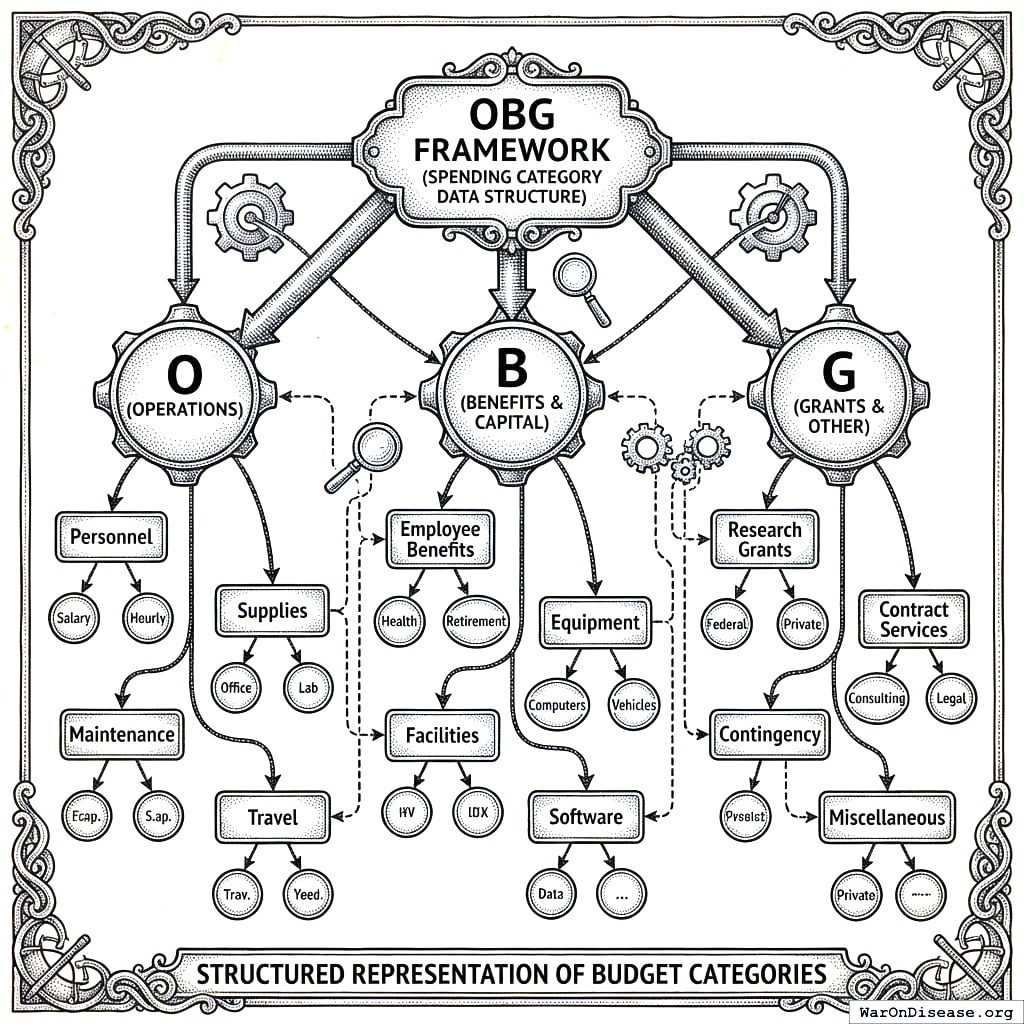
The OBG framework uses a structured representation of budget categories:
-- Spending categories
spending_categories (
    id, name, parent_category_id,
    spending_type, -- 'program', 'transfer', 'investment', 'regulatory'
    outcome_categories, -- which welfare outcomes this affects
    current_spending_usd, fiscal_year,
    data_source, last_updated
)

-- Cross-country spending data
reference_spending (
    category_id, country_code, year,
    spending_usd, spending_per_capita,
    spending_pct_gdp, population, gdp,
    data_source
)

-- Optimal spending level estimates
osl_estimates (
    category_id, estimation_method,
    osl_usd, osl_per_capita, osl_pct_gdp,
    confidence_interval_low, confidence_interval_high,
    evidence_grade, bis_score,
    methodology_notes, last_updated
)

-- Gap analysis
spending_gaps (
    category_id, current_spending_usd,
    osl_usd, gap_usd, gap_pct,
    priority_score, -- gap * BIS confidence
    recommended_action
)
Two Methods for OSL Estimation
| Method | Use Case | Data Required | Strengths | Limitations |
|---|---|---|---|---|
| Diminishing returns modeling | Categories with cross-country spending-outcome data | Effect estimates at multiple spending levels | Theoretically grounded, finds optimal “knee” | Requires sufficient country variation |
| Cost-effectiveness threshold | Health/life-saving interventions | Cost per QALY/DALY, willingness-to-pay | Links to standard health economics12 | Limited to monetizable outcomes |
Each method is detailed below.
Diminishing Returns Modeling
The Core Concept
The fiscal multiplier literature establishes that spending effects vary systematically with scale13,14. At low spending levels, each additional dollar produces substantial welfare gains. At high spending levels, marginal returns diminish. The OSL is where marginal return equals opportunity cost.
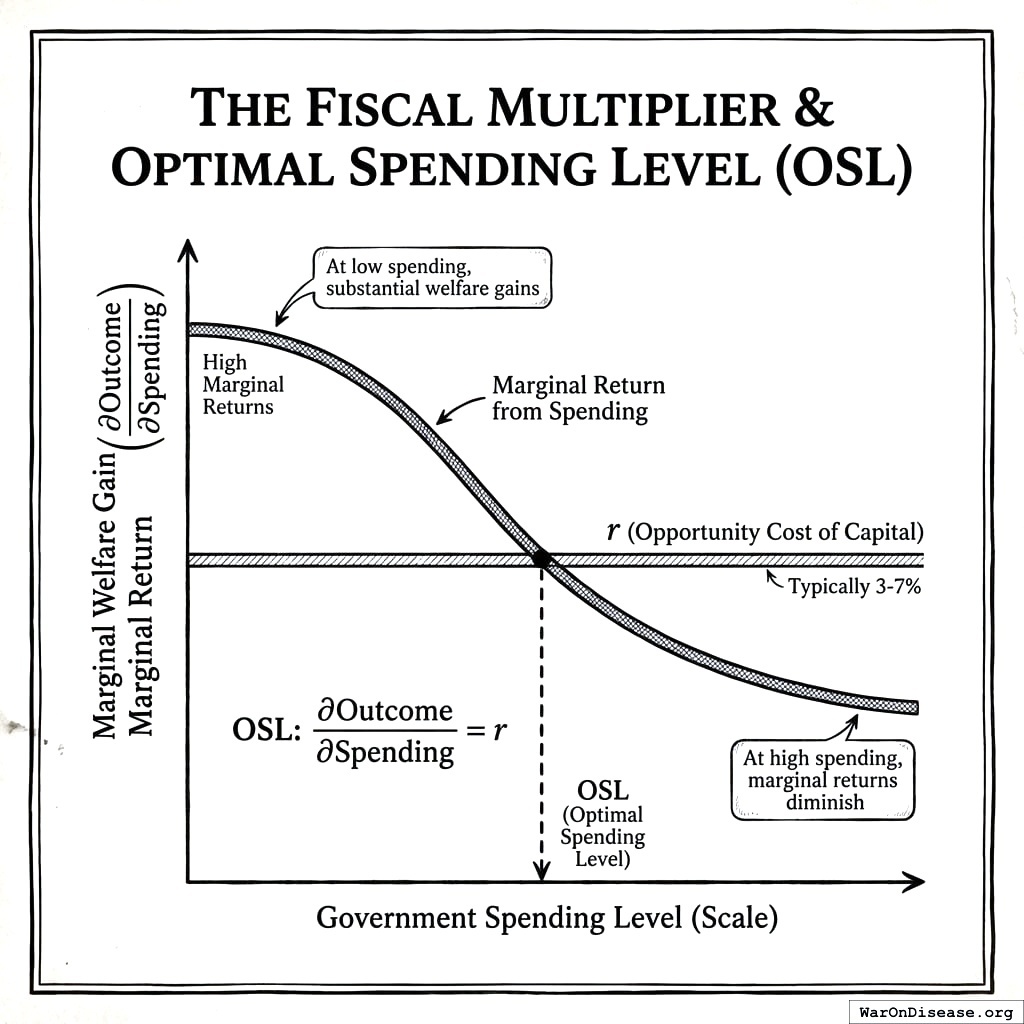
\[ \text{OSL}: \frac{\partial \text{Outcome}}{\partial \text{Spending}} = r \]
Where \(r\) is the discount rate or opportunity cost of capital (typically 3-7%).
Finding the “Knee” of the Curve
Empirically, we look for the point where the outcome-spending relationship flattens:
Outcome
   ^
   |                    ___________
   |                 __/
   |               _/
   |             _/
   |           _/   <- OSL is around here
   |         _/
   |       _/
   |     _/
   |   _/
   | _/
   |/
   +-----------------------------------> Spending
         Low            High
Estimation Methods
1. Nonlinear regression on cross-country data
Fit diminishing returns functions:
\[ \text{Outcome} = \alpha + \beta \cdot \log(\text{Spending}) + \epsilon \]
Or with saturation:
\[ \text{Outcome} = \alpha + \beta \cdot \frac{\text{Spending}}{\text{Spending} + \gamma} \]
Where \(\gamma\) is the half-saturation constant.
2. Piecewise linear estimation
Estimate separate slopes for different spending ranges to identify where returns diminish.
3. Meta-regression of effect estimates
If multiple studies estimate effects at different spending levels, meta-regression can identify how effects vary with baseline spending. The credibility of such estimates depends critically on identification strategy15.
Worked Example: K-12 Education Spending
Primary metric affected: Real after-tax median income growth (via higher wages from improved skills).
16 exploited court-ordered school finance reforms to estimate causal effects of K-12 spending. Key finding: a 10% increase in per-pupil spending increases adult earnings by 7% for students from low-income families.
Does this effect diminish at higher spending levels?
Evidence from cross-state variation suggests:
| Baseline spending (per pupil) | Effect of 10% increase | Implied marginal return |
|---|---|---|
| $8,000 | +8% earnings | $0.80 per $1 |
| $12,000 | +5% earnings | $0.50 per $1 |
| $16,000 | +3% earnings | $0.30 per $1 |
| $20,000 | +1% earnings | $0.10 per $1 |
OBG estimation: At $16,000/pupil, the marginal return (~0.30) roughly equals the social discount rate. This suggests:
- Current US average: ~$15,000/pupil
- OSL: ~$16,000-$18,000/pupil (modest underinvestment)
- Gap: ~$50B nationally
Evidence grade: B (strong causal identification, moderate extrapolation uncertainty)
Worked Example: Pragmatic Clinical Trials
The Highest-Return Public Investment
Metrics affected: Both real after-tax median income growth (via reduced healthcare costs and improved productivity) and median healthy life years (via better treatments). This dual impact contributes to the exceptionally high returns.

Pragmatic clinical trials represent perhaps the single highest-return category of public investment identified in the literature. While vaccinations return 13:1 and early childhood education returns 4:1, pragmatic trials demonstrate benefit-cost ratios of 439 (90% CI: 321-600):117.
The UK’s RECOVERY trial demonstrated this dramatically during COVID-19: it cost approximately $500 (95% CI: $400-$2,500) versus $41,000 (95% CI: $20,000-$120,000) for traditional Phase 3 trials, a 82x (90% CI: 21.4x-195x) cost reduction18. This single trial identified dexamethasone as a life-saving treatment, preventing an estimated 1 million deaths globally.
OSL Estimation
Pragmatic trials represent an innovation frontier where no country has achieved optimal investment. We estimate OSL from cost-effectiveness analysis:
- Unmet medical need: Approximately 2.88 billion DALYs/year (90% CI: 2.63 billion DALYs/year-3.12 billion DALYs/year) from conditions lacking adequate treatment
- Cost per DALY averted: Pragmatic trials cost $929 (95% CI: $929-$1,400) (ADAPTABLE trial) vs. $41,000 (95% CI: $20,000-$120,000) traditional
- Scale-up potential: Current global clinical trial spending is approximately $60 billion (95% CI: $50 billion-$75 billion)/year, but only ~$500M goes to pragmatic/embedded designs
| Data Point | Value | Source |
|---|---|---|
| Current pragmatic trial spending (US) | ~$500M | NIH Common Fund |
| Traditional trial spending (global) | Industry + NIH | |
| Cost per patient (pragmatic) | ADAPTABLE trial | |
| Cost per patient (traditional Phase 3) | Industry average | |
| Cost reduction factor | 44.1x (90% CI: 12.8x-210x) | Calculated |
Diminishing Returns Analysis
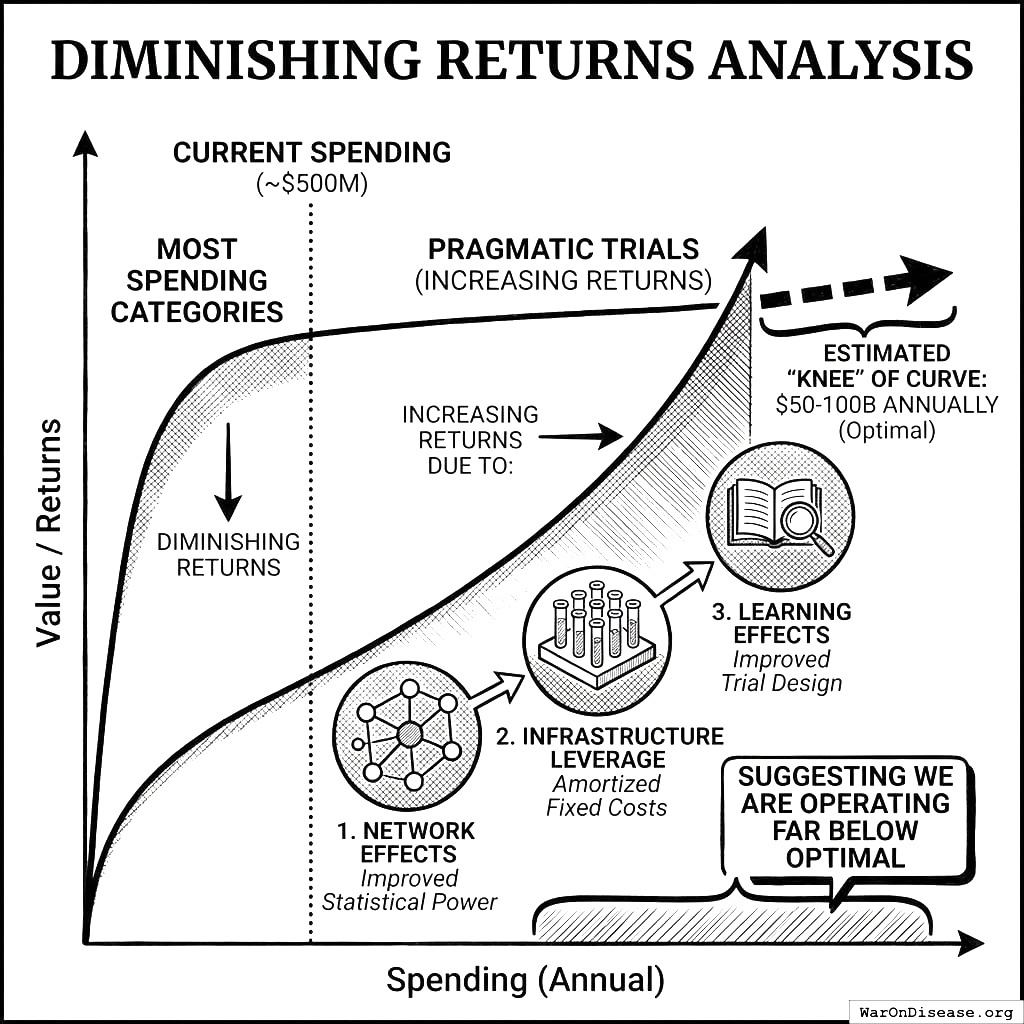
Unlike most spending categories, pragmatic trials show increasing returns at current spending levels due to:
- Network effects: Each additional participant improves statistical power for all trials
- Infrastructure leverage: Platform trials amortize fixed costs across multiple interventions
- Learning effects: Evidence accumulation improves trial design efficiency
The “knee” of the diminishing returns curve is estimated at $50-100B annually (vs. current ~$500M), suggesting we are operating far below optimal.
Cost-Effectiveness Calculation
Using standard health economics methodology:
| Component | Value | Calculation |
|---|---|---|
| Cost per pragmatic trial participant | ADAPTABLE benchmark | |
| QALYs gained per participant | 0.05-0.2 | Evidence generation value |
| Cost per QALY | $4,600-$18,600 | Well below $50K threshold |
| Scale-up population | 50M patients/year | 10% of treatable conditions |
| OSL estimate | $50B/year | Conservative |
Gap Analysis
| Metric | Value |
|---|---|
| Current spending (pragmatic trials) | ~$500M |
| OSL | $50B |
| Gap | +$49.5B (99x underinvestment) |
| Gap % of current | +9,900% |
| Opportunity cost | 439 (90% CI: 321-600):1 foregone returns |
Evidence grade: A (RCT evidence from RECOVERY, ADAPTABLE; strong theoretical foundation)
Why This Category Dominates
Pragmatic clinical trials have the highest priority score of any category analyzed:
\[ \text{Priority} = |\text{Gap}| \times \text{BIS} = \$49.5B \times 0.90 = 44.6 \]
Among categories requiring increased investment, this is the highest priority score, exceeding outcome-funded R&D (31.5), vaccinations (25.7), and early childhood (17.0). Military spending has a larger absolute priority score (195.5) due to its massive gap, but represents overinvestment requiring reduction.
Cost-Effectiveness Threshold Analysis
The Standard Health Economics Approach
Cost-effectiveness analysis has become the standard framework for health resource allocation decisions9. The QALY (Quality-Adjusted Life Year) metric enables comparison across diverse health interventions by monetizing health outcomes at a consistent threshold19.
For health interventions, cost-effectiveness analysis provides OSL estimates:
\[ \text{OSL} = \sum_{\text{interventions}} \text{Scale}_i \times \text{Cost}_i \quad \text{where } \frac{\text{Cost}_i}{\text{QALY}_i} < \text{WTP} \]
Where:
- \(\text{Scale}_i\) = target population for intervention \(i\)
- \(\text{Cost}_i\) = per-person cost of intervention \(i\)
- \(\text{QALY}_i\) = QALYs gained per person from intervention \(i\)
- \(\text{WTP}\) = willingness-to-pay threshold (typically $50K-$150K per QALY)
Building Up from Intervention-Level Data
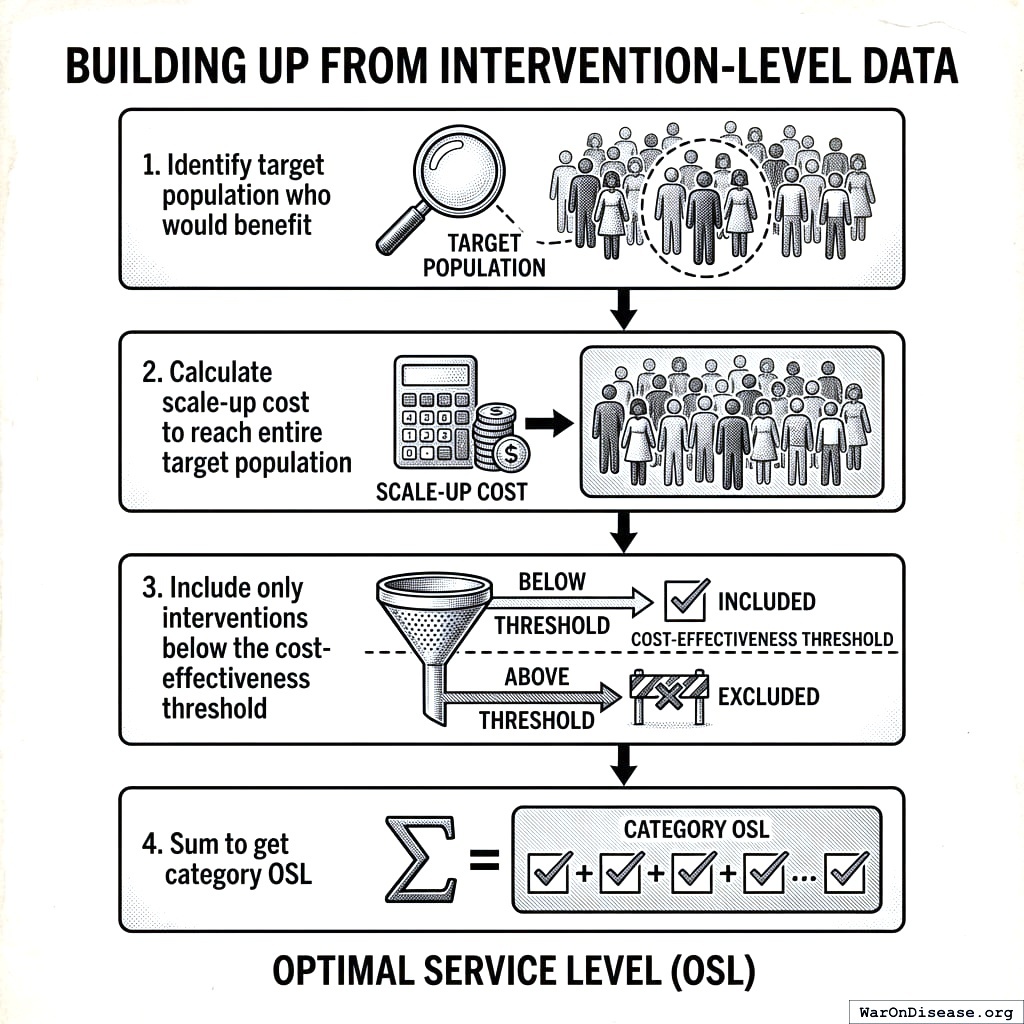
For each health intervention with cost-effectiveness data:
- Identify target population who would benefit
- Calculate scale-up cost to reach entire target population
- Include only interventions below the cost-effectiveness threshold
- Sum to get category OSL
Worked Example: Vaccinations
Primary metric affected: Median healthy life years (via disease prevention and mortality reduction).
Vaccinations represent one of the highest-return public health investments, with estimated returns of 44:1 for routine childhood immunization20,21. The economic benefits include avoided medical costs, productivity gains, and reduced mortality22.
Cost-effectiveness estimates from CEA Registry and CDC vaccination cost studies. QALY estimates reflect average health gains across target populations; costs include vaccine acquisition, administration, and program overhead.
| Intervention | Target pop. | Cost/person | QALY/person | Cost/QALY | Source | Include? |
|---|---|---|---|---|---|---|
| Childhood routine | 4M births | $500 | 0.1 | $5,000 | CDC VFC | Yes |
| HPV vaccination | 4M teens | $300 | 0.05 | $6,000 | CEA Registry | Yes |
| Flu (elderly) | 50M elderly | $40 | 0.01 | $4,000 | CDC | Yes |
| Shingles | 40M eligible | $200 | 0.02 | $10,000 | CEA Registry | Yes |
| COVID boosters | 100M adults | $30 | 0.005 | $6,000 | CDC | Yes |
All interventions fall well below the conventional $50,000-$150,000 per QALY cost-effectiveness threshold, indicating strong economic justification for full scale-up.
OBG calculation:
- Childhood routine: 4M × $500 = $2.0B
- HPV: 4M × $300 = $1.2B
- Flu (elderly): 50M × $40 = $2.0B
- Shingles: 40M × $200 = $8.0B
- COVID boosters: 100M × $30 = $3.0B
- Total OSL: ~$16B (vs. current ~$8B)
Gap: +$8B (underinvestment)
Evidence grade: A (RCT evidence for most vaccines, well-established cost-effectiveness)
Budget Impact Score (BIS)
The Budget Impact Score measures confidence in each category’s OSL estimate based on the quality and quantity of causal evidence. The scoring methodology draws on the established evidence hierarchy from the econometrics literature15,23.
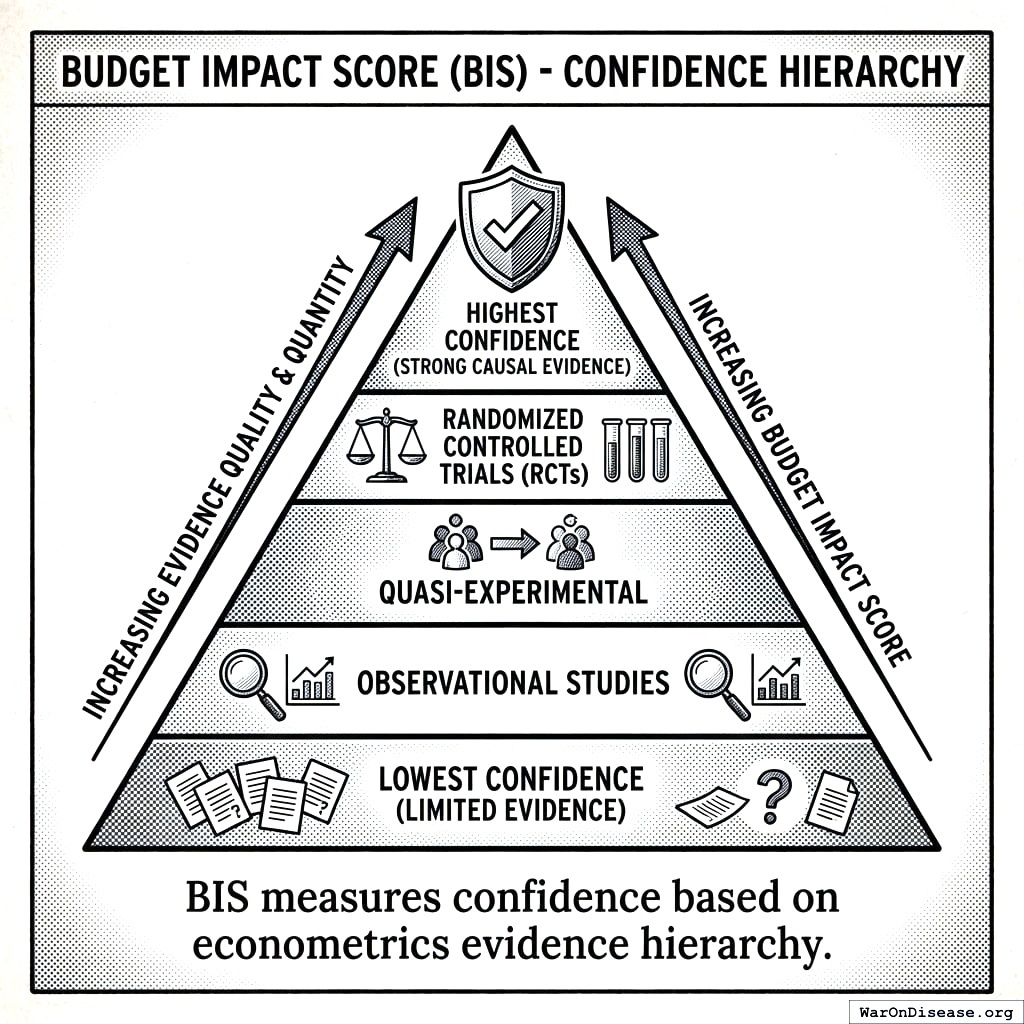
BIS Calculation
For each spending category \(i\):
Step 1: Gather effect estimates
Collect all available causal effect estimates \(\{\beta_{i,1}, \beta_{i,2}, ..., \beta_{i,n_i}\}\) from the econometric literature.
Step 2: Compute quality weights
| Identification Method | Quality Weight (\(w^Q\)) |
|---|---|
| Randomized controlled trial | 1.00 |
| Natural experiment (difference-in-differences, regression discontinuity) | 0.85 |
| Instrumental variables | 0.70 |
| Panel with fixed effects | 0.55 |
| Cross-sectional regression | 0.25 |
Step 3: Compute precision weights
\[ w^P_j = \frac{1}{\text{SE}(\beta_j)^2} \]
Step 4: Compute recency weights
\[ w^R_j = e^{-0.03(t_{now} - t_j)} \]
Step 5: Compute confidence score
\[ \text{BIS}_i = \min\left(1, \frac{\sum_j w^Q_j \cdot w^P_j \cdot w^R_j}{K}\right) \]
Where \(K\) is a calibration constant.
Evidence Grading from BIS
| BIS Range | Grade | Interpretation | OSL Confidence |
|---|---|---|---|
| 0.80 - 1.00 | A | Strong causal evidence | High - proceed with reallocation |
| 0.60 - 0.79 | B | Good evidence | Moderate - proceed with monitoring |
| 0.40 - 0.59 | C | Mixed evidence | Low - pilot before scaling |
| 0.20 - 0.39 | D | Weak evidence | Very low - research priority |
| 0.00 - 0.19 | F | Insufficient evidence | Unknown - cannot estimate OSL |
Gap Analysis and Priority Ranking
Computing Gaps
For each category \(i\):
\[ \text{Gap}_i = \text{OSL}_i - \text{Current}_i \]
- Gap > 0: Underinvestment (increase spending)
- Gap = 0: At optimal (maintain)
- Gap < 0: Overinvestment (decrease spending)
Priority Score
Prioritize reallocation by gap size weighted by confidence:
\[ \text{Priority}_i = |\text{Gap}_i| \times \text{BIS}_i \]
Categories with large gaps AND high confidence should be addressed first.
Illustrative Example: Priority Ranking
The following uses the same illustrative data from the dashboard example above. OSL estimates for pragmatic trials, vaccinations, and K-12 education are derived in Sections 5-7. Other OSL values use cross-country benchmarking. BIS scores summarize available causal evidence quality.
| Category | Current | OSL | Gap | BIS | Inc | Hlth | Priority | Action |
|---|---|---|---|---|---|---|---|---|
| Pragmatic trials | $0.5B | $50B | +$49.5B | 0.90 | ++ | +++ | 44.6 | Scale 100x |
| Outcome-funded R&D | $45B | $90B | +$45B | 0.70 | ++ | ++ | 31.5 | Increase |
| Vaccinations | $8B | $35B | +$27B | 0.95 | + | +++ | 25.7 | Increase |
| Early childhood | $50B | $70B | +$20B | 0.85 | +++ | + | 17.0 | Increase |
| Military | $850B | $459B | -$391B | 0.50 | − | − | 195.5 | Decrease |
| Ag subsidies | $25B | $0B | -$25B | 0.90 | − | − | 22.5 | Eliminate |
Inc = effect on real after-tax median income growth. Hlth = effect on median healthy life years. Scale: +++ strong, ++ moderate, + weak, − negative.
Reallocation plan: Cut military discretionary (-$391B) and agricultural subsidies (-$25B) to fund pragmatic clinical trials (+$49.5B), outcome-funded R&D (+$45B), vaccinations (+$27B), and early childhood (+$20B). Pragmatic trials have the highest priority score among positive-gap categories due to extreme underinvestment combined with strong evidence, and they improve both welfare metrics.
Multi-Unit Reporting
The Problem with Abstract Scores
Composite scores (like 0-1 BIS values) obscure interpretability. Policymakers and citizens understand dollars, lives, and years - not abstract indices.
Reporting at Multiple Levels
| Level | Units | Use Case | Example |
|---|---|---|---|
| 0. Core metrics | pp/year income growth, healthy life years | Primary welfare outcomes | “+0.1 pp income growth, +0.05 healthy years” |
| 1. Natural | Domain-specific | Interpretation within domain | “Education: $2,100/student gap” |
| 2. Monetized | $ equivalent | Cross-domain comparison | “Expected welfare gain: $4.00 per $1” |
| 3. Health | QALYs/DALYs | Health-weighted comparison | “12,000 QALYs per $1B invested” |
| 4. Composite | 0-1 score | Ranking when monetization uncertain | “BIS = 0.85” |
Level 0 (Core Metrics) reports expected changes to the two welfare metrics directly. All other levels are derived from or convertible to these core outcomes. QALYs (Level 3) translate directly to median healthy life years. Monetized values (Level 2) combine income effects with health effects valued at standard rates.
Conversion Factors
| Conversion | Value | Source | Notes |
|---|---|---|---|
| Value of Statistical Life (VSL) | ~$10M | EPA, DOT | US regulatory standard |
| Value per QALY | $50K-$150K | ICER, WHO | Context-dependent |
| QALY → $ | $100K/QALY | Mid-range estimate | For cross-domain |
| Life-year → QALY | ~0.8-1.0 | Age/health adjusted | Quality weighting |
Worked Example: Multi-Unit Output
Category: Early Childhood Education
| Unit Level | Value | Interpretation |
|---|---|---|
| Natural | +$20B gap | Current: $50B, OSL: $70B |
| Per-child | +$833/child gap | 24M children |
| Monetized ROI | 4:1 NPV return | 24 |
| Health (QALYs) | +8K QALYs/year | Per $1B additional |
| Composite (BIS) | 0.85 | High-quality RCT evidence |
Recommendation: Moderate underinvestment with strong evidence. Closing the gap would yield ~$80B in NPV returns.
Quality Requirements and Validation
Minimum Thresholds for OBG Estimation
| Criterion | Minimum | Rationale |
|---|---|---|
| Reference countries | 5+ | Avoid outlier bias |
| Dose-response studies | 3+ | Identify diminishing returns |
| Causal effect estimates | 2+ | Cross-validate |
| Data recency | Within 10 years | Relevance |
| BIS for reallocation | > 0.40 | Sufficient confidence |
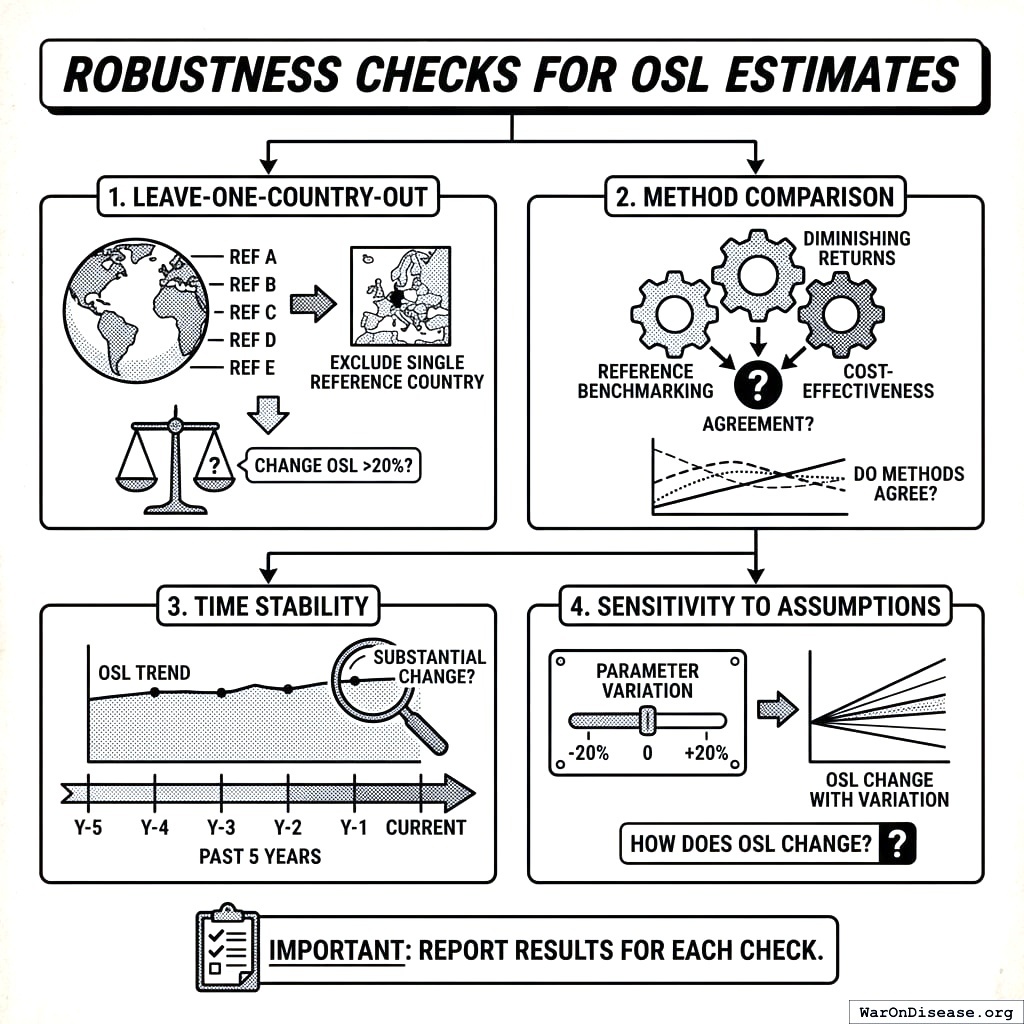
Robustness Checks
For each OSL estimate, report:
- Leave-one-country-out: Does excluding any single country change OSL by >20%?
- Method comparison: Do diminishing returns and cost-effectiveness methods agree?
- Time stability: Has OSL changed substantially over past 5 years?
- Sensitivity to assumptions: How does OSL change with ±20% parameter variation?
Interpreting Results
Gap Ranges and Recommended Actions
| Gap (% of current) | Interpretation | Recommended Action |
|---|---|---|
| > +50% | Severe underinvestment | Immediate scale-up |
| +20% to +50% | Moderate underinvestment | Phased increase |
| -10% to +20% | Near optimal | Monitor, fine-tune |
| -50% to -10% | Moderate overinvestment | Gradual reduction |
| < -50% | Severe overinvestment | Urgent reallocation |
What the Algorithm Cannot Tell You
| Factor | OBG Captures | OBG Does Not Capture |
|---|---|---|
| Evidence-optimal spending level | Yes | |
| Confidence in estimates | Yes | |
| Direction of reallocation | Yes | |
| Political feasibility | No | |
| Implementation capacity | No | |
| Transition costs | No | |
| Distributional effects | No | |
| Novel interventions | No |
OBG provides evidence-based targets. Political judgment is still required for implementation strategy.
Pilot Program Prioritization
Value of Information for Uncertain Categories
Categories with low BIS but potentially high returns warrant research investment:
\[ \text{VOI}_i = \text{Potential Gap}_i \times (1 - \text{BIS}_i) \times P(\text{high return}) \]
High-VOI categories should receive pilot funding to generate better evidence.
Recommended Pilot Designs
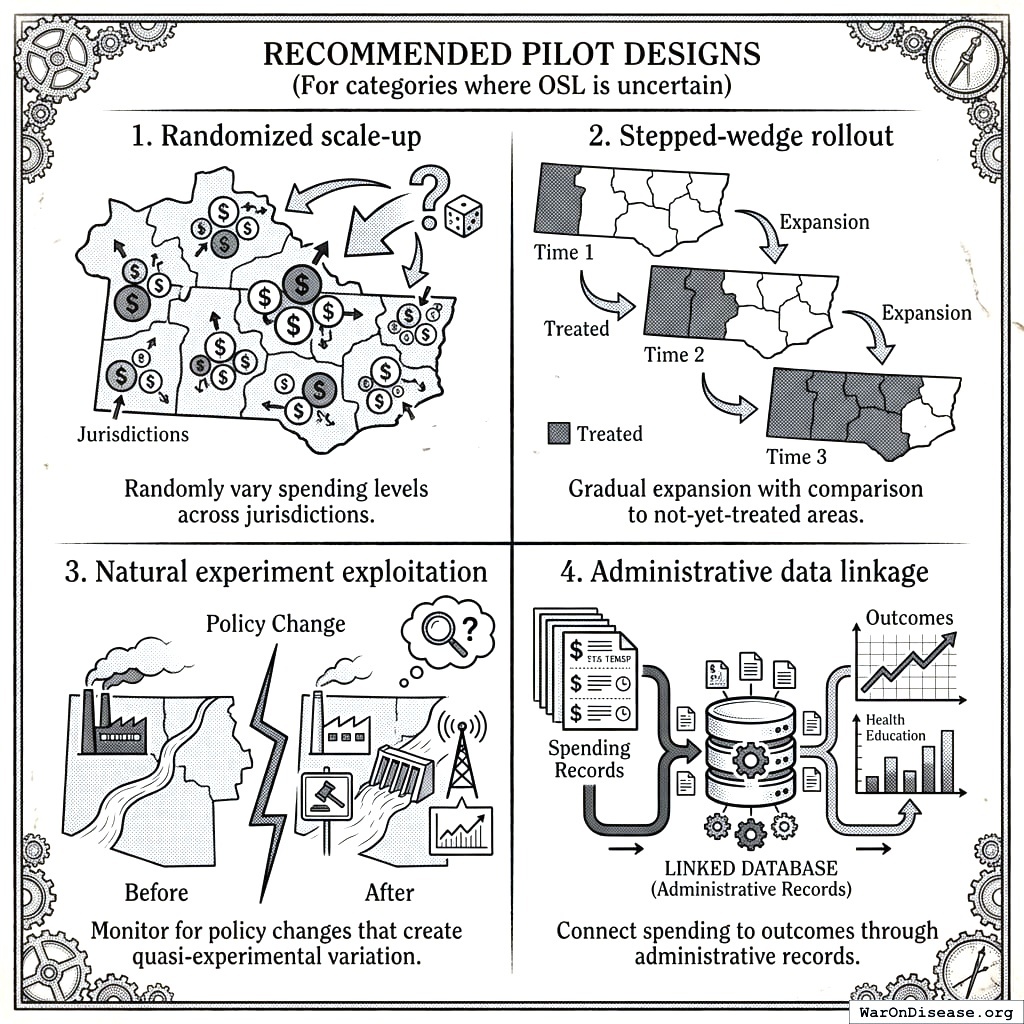
For categories where OSL is uncertain:
- Randomized scale-up: Randomly vary spending levels across jurisdictions
- Stepped-wedge rollout: Gradual expansion with comparison to not-yet-treated areas
- Natural experiment exploitation: Monitor for policy changes that create quasi-experimental variation
- Administrative data linkage: Connect spending to outcomes through administrative records
Learning Feedback Loop
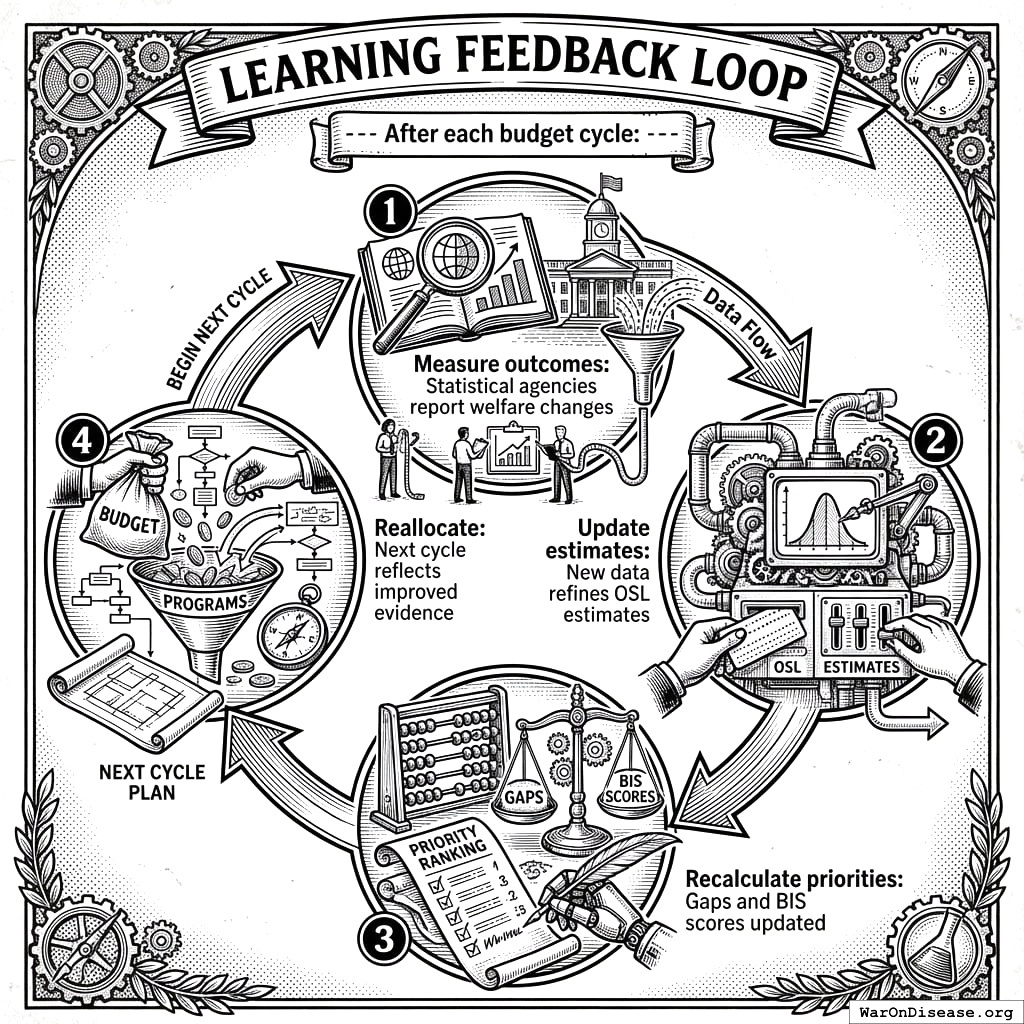
After each budget cycle:
- Measure outcomes: Statistical agencies report welfare changes
- Update estimates: New data refines OSL estimates
- Recalculate priorities: Gaps and BIS scores updated
- Reallocate: Next cycle reflects improved evidence
Data Sources
Cross-Country Databases
International organizations maintain standardized cross-country spending and outcome data essential for diminishing returns analysis. The OECD provides the most comprehensive harmonized data for high-income countries10.
| Database | Coverage | URL | Use Case |
|---|---|---|---|
| OECD iLibrary | 38 OECD members | oecd-ilibrary.org25 | Education, health, social spending |
| World Bank WDI | 217 countries | data.worldbank.org26 | Broad spending and outcomes |
| SIPRI | Global | sipri.org27 | Military spending |
| WHO GHED | 194 countries | who.int/data/gho28 | Health expenditure |
| UNESCO UIS | Global | uis.unesco.org29 | Education spending |
Cost-Effectiveness Databases
| Database | Coverage | URL | Use Case |
|---|---|---|---|
| CEA Registry | 8,000+ analyses | cearegistry.org30 | Health cost-effectiveness |
| Disease Control Priorities | LMICs | dcp-3.org31 | Global health priorities |
| Cochrane Library | 8,000+ reviews | cochranelibrary.com32 | Health intervention effects |
| Copenhagen Consensus | Development | copenhagenconsensus.com33 | Development priorities |
These databases enable systematic ranking of interventions by cost-effectiveness. For example, deworming programs consistently rank among the most cost-effective health interventions, with costs as low as $30-50 per DALY averted34.
US Budget Data
| Source | Coverage | URL | Use Case |
|---|---|---|---|
| OMB Historical Tables | 1789-present | whitehouse.gov/omb35 | Federal spending |
| CBO Budget Analyses | Federal | cbo.gov36 | Fiscal impact scoring8 |
| USASpending | Federal awards | usaspending.gov37 | Program-level detail |
| Census of Governments | State & local | census.gov38 | Subnational spending |
Limitations
Diminishing Returns Uncertainty
- Functional form: True relationship may not match assumed function
- Extrapolation: Estimating returns outside observed spending range
- Interaction effects: Returns may depend on other spending categories
Mitigation: Report confidence intervals, use multiple functional forms, acknowledge extrapolation limits.
Implementation Capacity
Higher spending may not translate to outcomes if implementation capacity is lacking.
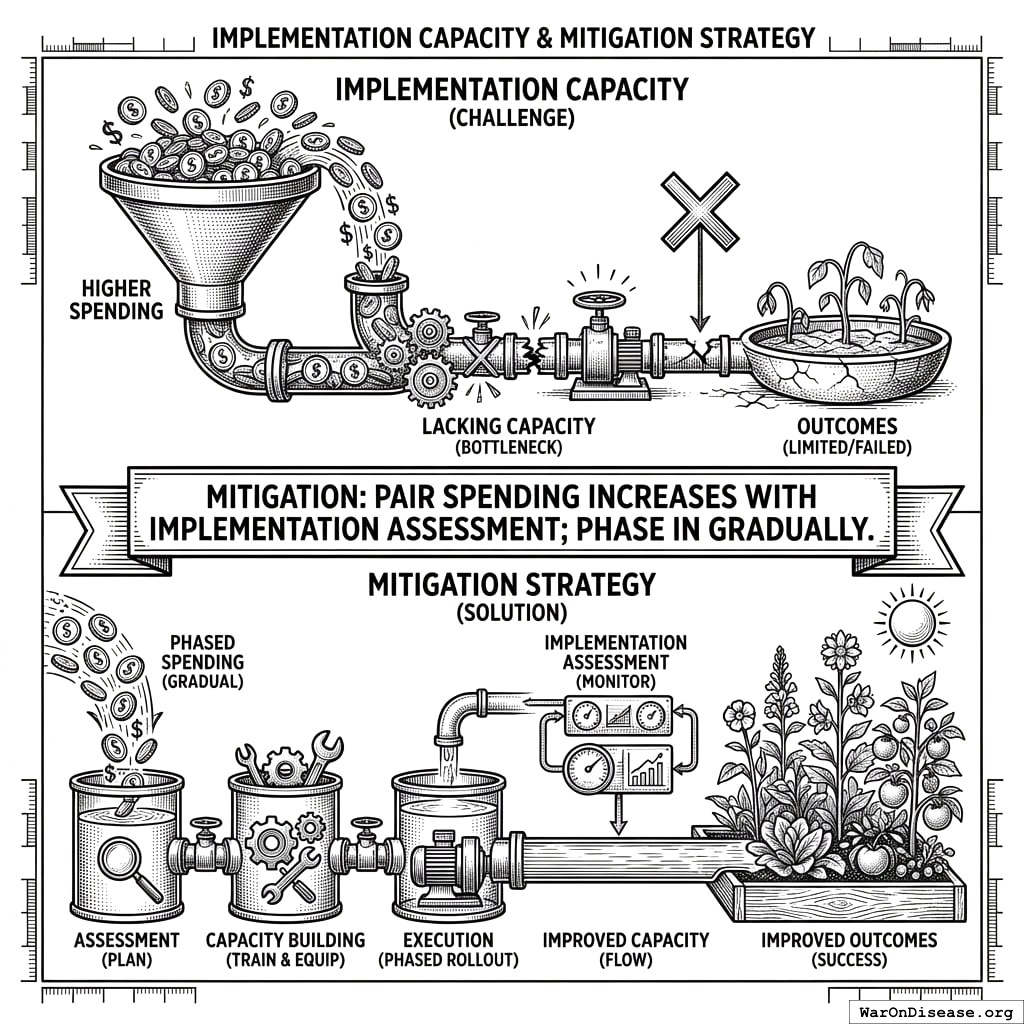
Mitigation: Pair spending increases with implementation assessment; phase in gradually.
Benchmarking Framework
This section defines how OBG should be benchmarked against historical and prospective budget outcomes.
Retrospective Validation
Question: Did jurisdictions that moved toward OSL achieve better outcomes than those that diverged?

Method: 1. Compute OSL for past periods using only data available at that time (to avoid lookahead bias) 2. Identify jurisdictions that moved toward/away from OSL 3. Compare subsequent outcomes using difference-in-differences or synthetic control methods39
Example: US State Education Spending 2000-2015
A retrospective analysis can examine whether states that moved toward education OSL (estimated from high-performing states like Massachusetts and Minnesota) subsequently showed improved test scores and graduation rates relative to states that diverged.
Challenges:
- Confounding from simultaneous policy changes
- Limited variation in spending changes within countries
- Outcome measurement lags (education effects take years to materialize)
Prospective Validation
Question: Do OBG-guided reallocations improve outcomes going forward?
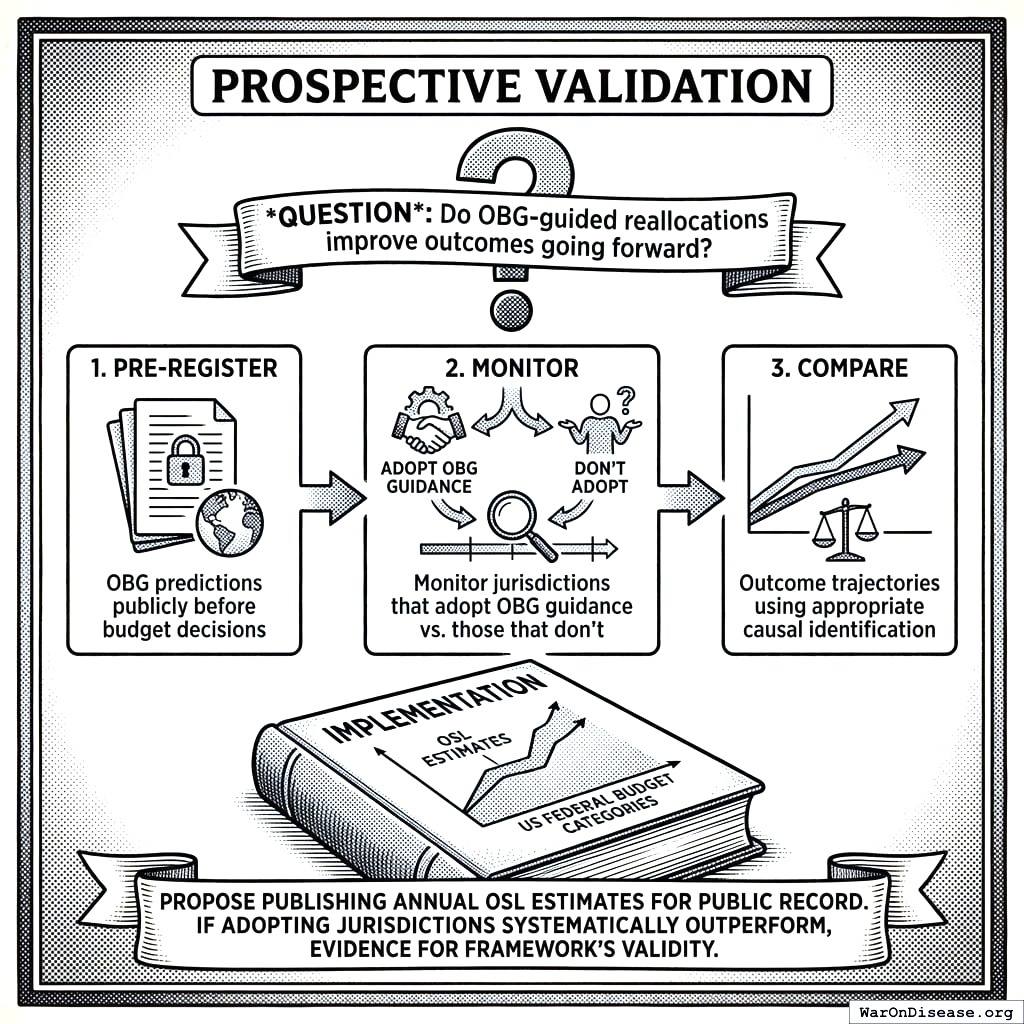
Method: 1. Pre-register OBG predictions publicly before budget decisions 2. Monitor jurisdictions that adopt OBG guidance vs. those that don’t 3. Compare outcome trajectories using appropriate causal identification
Implementation: Publish annual OSL estimates for US federal budget categories, creating a public record for prospective benchmarking. If jurisdictions that adopt OBG guidance systematically outperform those that do not, the framework is doing its job.
Success Metrics
| Metric | Definition | Target | Interpretation |
|---|---|---|---|
| Gap reduction | Did spending move toward OSL? | > 50% of gap closed in 10 years | Tests political feasibility |
| Outcome improvement | Did welfare metrics improve more in OBG-following jurisdictions? | > 10% relative improvement | Tests welfare prediction accuracy |
| Prediction accuracy | Did estimated returns match actual returns? | Correlation r > 0.5 | Tests underlying model |
| Cross-method consistency | Do diminishing returns and cost-effectiveness methods converge? | Agreement within 30% | Tests methodological robustness |
Evidence Base and Benchmarking
OBG rests on the underlying studies cited throughout (e.g.,16 for education,20 for vaccinations) plus a continuous benchmarking program:
- Data collection: Longitudinal spending and outcome data across jurisdictions
- Historical OSL estimation: Compute past OSL using only contemporaneously available data
- Causal analysis: Identify spending → outcome effects with strong quasi-experimental designs
- Publication: Publish pre-registered benchmark studies and annual scorecards
Sensitivity Analysis
Parameter Sensitivity
| Parameter | Default | Test Range | Impact on OSL |
|---|---|---|---|
| Country data set | All OECD | OECD + G20, High-income only | ±15% |
| Discount rate | 5% | 3-7% | ±20% |
| BIS confidence threshold | 0.40 | 0.30-0.60 | Category inclusion |
| Recency decay rate | 0.03/year | 0.01-0.05 | Estimate weights |
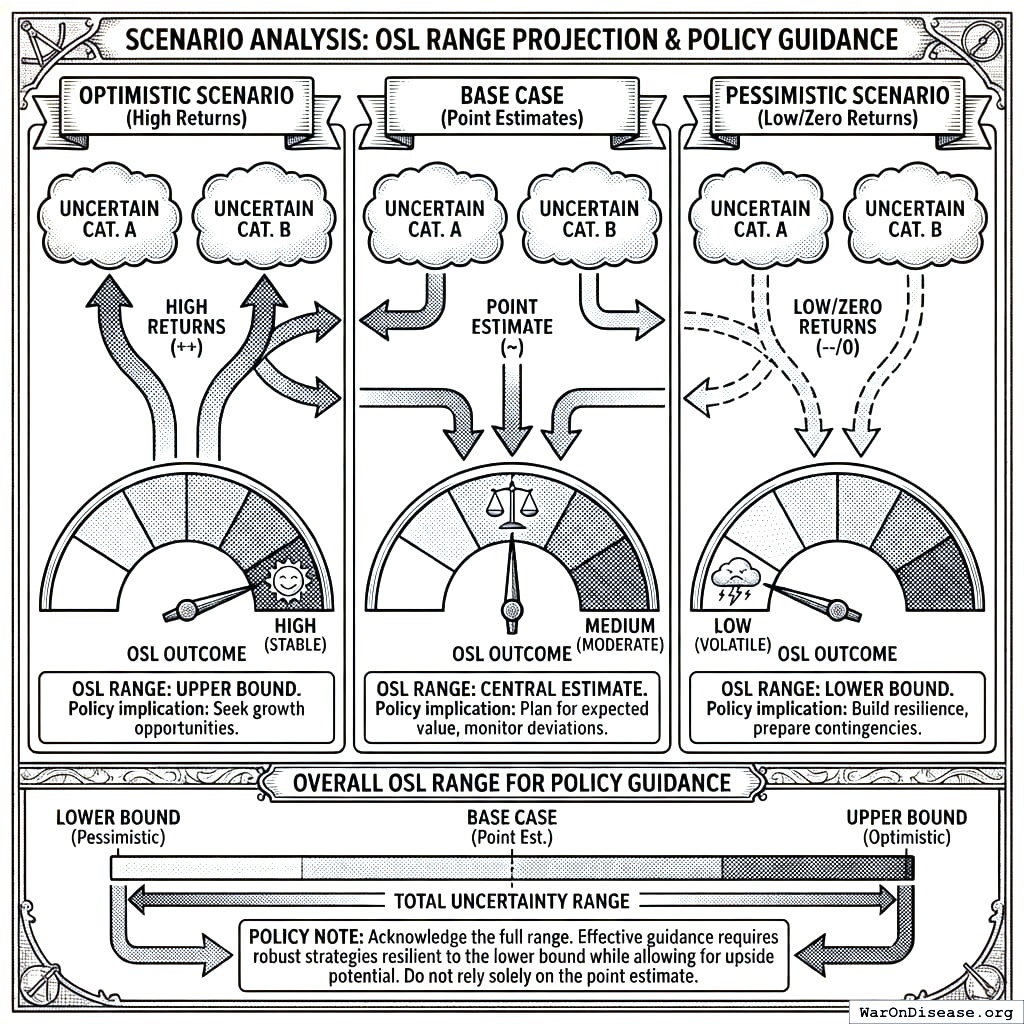
Scenario Analysis
Optimistic scenario: All uncertain categories have high returns Pessimistic scenario: Uncertain categories have low/zero returns Base case: Use point estimates
Report OSL range across scenarios for policy guidance.
Conclusion
The Optimal Budget Generator framework provides a systematic, evidence-based approach to budget allocation. Unlike marginal-return frameworks that can justify infinite spending on high-return categories, OBG recognizes that every category has an optimal level - like the Recommended Daily Allowance for nutrients.
The framework answers three questions:
- What is the target? OBG provides evidence-based spending levels for each category
- How far are we? Gap analysis shows where current spending diverges from optimal
- How confident are we? BIS scores evidence quality so policymakers know which OSL estimates are reliable
Even with imperfect evidence, systematically moving from severe misallocation (military 100% above OSL, vaccinations 75% below OSL) toward evidence-based targets should produce substantially larger welfare gains than current lobbying-driven allocation achieves.
Acknowledgments
The author thanks seminar participants and anonymous reviewers for helpful comments and suggestions. All errors remain the author’s own.
Appendix A: Analysis Workflow
Complete OBG Analysis Pipeline
+-------------------------------------------------------------+
|                    OBG ANALYSIS WORKFLOW                      |
+-------------------------------------------------------------+

Phase 1: DATA COLLECTION
-------------------------
1. Budget data ingestion
   +-- Pull current spending by category (OMB, USASpending)

   +-- Normalize categories to standard taxonomy
   +-- Identify subcategories for detailed analysis
   +-- Flag data quality issues

2. Cross-country spending data
   +-- Pull spending data from OECD, World Bank
   +-- Include all comparable countries
   +-- Normalize to per-capita and % GDP
   +-- Prepare for regression analysis

3. Effect estimate data
   +-- Search systematic reviews and meta-analyses
   +-- Extract effect sizes with standard errors
   +-- Code study quality (RCT, natural experiment, etc.)
   +-- Build literature database by category

Phase 2: OSL ESTIMATION
-----------------------
4. Diminishing returns modeling
   +-- Fit nonlinear spending-outcome functions
   +-- Identify "knee" of curve
   +-- Calculate marginal returns at current spending
   +-- Estimate optimal level

5. Cost-effectiveness analysis (health/life-saving)
   +-- Identify interventions below CE threshold
   +-- Calculate scale-up costs
   +-- Sum to category OSL
   +-- Document assumptions

6. Method reconciliation
   +-- Compare OSL estimates across methods
   +-- Weight by method reliability
   +-- Produce consensus OSL estimate
   +-- Flag discrepancies

Phase 3: EVIDENCE QUALITY
-------------------------
7. BIS calculation
   +-- Compute quality weights per study
   +-- Compute precision weights
   +-- Compute recency weights
   +-- Aggregate to category BIS

8. Evidence grading
   +-- Assign A-F grade based on BIS
   +-- Document key evidence
   +-- Identify research gaps
   +-- Flag high-uncertainty categories

Phase 4: GAP ANALYSIS
---------------------
9. Compute gaps
    +-- Gap = OSL - Current
    +-- Calculate % gap
    +-- Classify as under/over/optimal
    +-- Apply BIS weighting

10. Priority ranking
    +-- Priority = |Gap| × BIS
    +-- Rank categories
    +-- Identify reallocation pairs
    +-- Estimate welfare gains

Phase 5: OUTPUT GENERATION
--------------------------
11. Multi-unit reporting
    +-- Natural units ($/capita, % GDP)
    +-- Monetized (ROI, opportunity cost)
    +-- Health units (QALYs where applicable)
    +-- Composite (BIS, evidence grade)

12. Sensitivity analysis
    +-- Vary key parameters
    +-- Test country data subsets
    +-- Report OSL ranges
    +-- Identify robust conclusions

13. Documentation
    +-- Generate category reports
    +-- Create methodology audit trail
    +-- Version control estimates
    +-- Publish to dashboard/API
Appendix B: Glossary
Core Concepts
- Optimal Budget Generator (OBG): The framework/methodology for generating integrated budget recommendations based on evidence of spending-outcome relationships. OBG accounts for the zero-sum nature of budget allocation and produces Optimal Spending Level (OSL) estimates for each category.
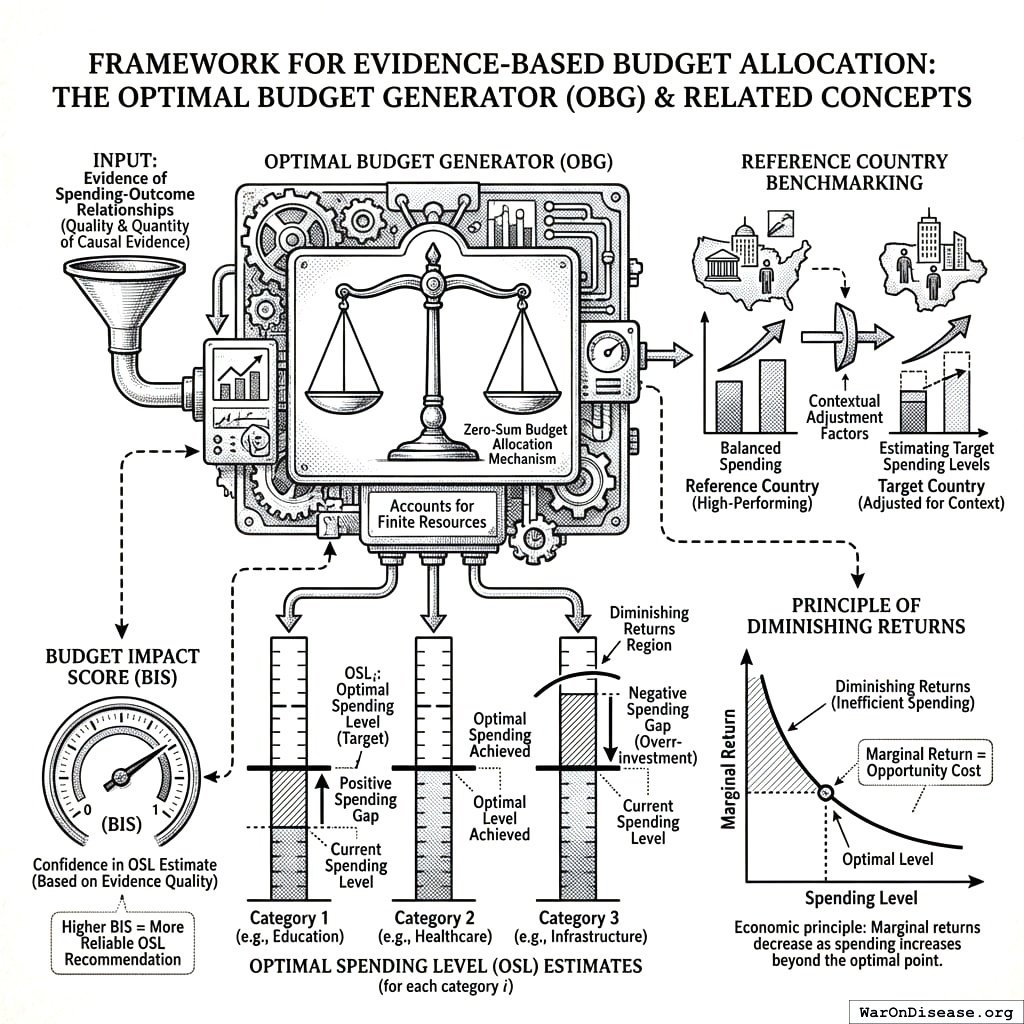
Optimal Spending Level (OSL): The evidence-based target spending level for each category, produced by the OBG framework. \(\text{OSL}_i\) represents the optimal spending level for category \(i\). Below OSL indicates underinvestment; above OSL indicates diminishing returns.
Budget Impact Score (BIS): A 0-1 score measuring confidence in each category’s OSL estimate based on the quality and quantity of causal evidence. Higher BIS indicates more reliable OSL recommendations.
Spending Gap: The difference between current spending and the evidence-based target for each category. Positive gaps indicate underinvestment; negative gaps indicate overinvestment.
Diminishing Returns: The economic principle that marginal returns to spending decrease as spending increases. The optimal level is where marginal return equals opportunity cost.
Estimation Methods
Cost-Effectiveness Threshold: The maximum acceptable cost per QALY (or other health outcome) for including an intervention in target calculations. Typically $50K-$150K per QALY.
Dose-Response Curve: The relationship between spending level (dose) and outcome (response). Used to identify diminishing returns and estimate optimal spending levels.
Evidence Quality
Quality Weight (\(w^Q\)): Weight assigned to a study based on identification strategy. RCTs receive 1.0; cross-sectional studies receive 0.25.
Precision Weight (\(w^P\)): Weight assigned based on standard error. More precise estimates receive higher weight.
Recency Weight (\(w^R\)): Weight assigned based on publication date. More recent studies receive higher weight via exponential decay.
Evidence Grade: Letter grade (A-F) summarizing confidence in each category’s target estimate. A = strong evidence; F = insufficient evidence.
Output Concepts
Priority Score: Product of gap magnitude and BIS. Used to rank categories for reallocation priority.
Value of Information (VOI): Expected benefit of additional research on uncertain categories. High-VOI categories warrant pilot funding.
Multi-Unit Reporting: Presenting results in natural units, monetized equivalents, health units, and composite scores for interpretability.
Appendix C: Illustrative Comparison to US Budget
This appendix applies the OBG methodology to the US discretionary budget as an illustrative exercise. “Current” figures reflect approximate FY2024 budget authority. OSL estimates for pragmatic trials, vaccinations, and K-12 education are derived from the worked examples in Sections 5-7. Other OSL values integrate cross-country benchmarking and published cost-effectiveness evidence. BIS scores summarize the strength of the causal evidence.
Illustrative US Discretionary Budget vs. OSL Targets
| Category | Current (\(B) | OSL (\)B) | Gap ($B) | Gap % | BIS | Inc | Hlth | Priority | |
|---|---|---|---|---|---|---|---|---|
| Military (discretionary) | 850 | 459 | -391 | -46% | 0.50 | − | − | 195 |
| Non-military discretionary | 915 | 1,350 | +435 | +48% | 0.65 | ++ | ++ | 283 |
| - Pragmatic clinical trials | 0.5 | 50 | +49.5 | +9,900% | 0.90 | ++ | +++ | 44.6 |
| - Education | 80 | 120 | +40 | +50% | 0.75 | +++ | + | 30 |
| - Health (research) | 50 | 100 | +50 | +100% | 0.80 | + | +++ | 40 |
| - Vaccinations | 8 | 35 | +27 | +338% | 0.95 | + | +++ | 26 |
| - Basic research | 45 | 90 | +45 | +100% | 0.70 | ++ | ++ | 32 |
| - Infrastructure | 100 | 150 | +50 | +50% | 0.60 | ++ | + | 30 |
| - Early childhood | 50 | 70 | +20 | +40% | 0.85 | +++ | + | 17 |
| Agricultural subsidies | 25 | 0 | -25 | -100% | 0.90 | − | − | 23 |
Inc = effect on real after-tax median income growth. Hlth = effect on median healthy life years. Scale: +++ strong positive, ++ moderate, + weak, − negative.
Key findings:
- Extreme underinvestment in pragmatic trials: At 9,900% below OSL with 439 (90% CI: 321-600):1 BCR, this is the single largest misallocation in the federal budget (see Section 6 for full derivation)
- Overinvestment in military spending: Military spending is ~$391B (46%) above OSL estimates based on cross-country benchmarking
- Underinvestment in outcomes: Vaccinations, outcome-funded R&D, and health research sit far below evidence-optimal levels
- Negative-return spending: Agricultural subsidies produce negative welfare effects per the cost-effectiveness literature
- Reallocation potential: The direction of reallocation runs from military and subsidies toward research, health, and education
Corresponding Author: Mike P. Sinn, Institute for Accelerated Medicine (m@warondisease.org)
Conflicts of Interest: The author declares no conflicts of interest.
Funding: This work received no external funding.
Data Availability: All data sources referenced in this paper are publicly available: OECD iLibrary (education, health spending), World Bank WDI (cross-country indicators), SIPRI Military Expenditure Database (defense spending), and CDC vaccination cost data. URLs are provided in the Data Sources section. A complete replication package including analysis code, data extraction scripts, and worked example calculations will be deposited in a public repository (GitHub/Zenodo) upon publication.
Ethics Statement: This is a methodological specification. No human subjects research was conducted.